Stereotactic radiosurgery (SRS) is generally considered for a vestibular schwannoma that is small to moderate in size (usually Koos grade I–III), has documented growth, and is not causing substantial brainstem compression or fourth-ventricle displacement. It is also an option for some larger tumors when there is no symptomatic mass effect, surgery carries unusual risk, or the patient strongly prefers to avoid resection.
Observation is usually preferred for an incidental, asymptomatic, stable small tumor with preserved cranial-nerve function. Large tumors producing brainstem compression, hydrocephalus, disabling symptoms, or major mass effect generally require microsurgical decompression rather than SRS. The decision depends on MRI findings, growth, hearing, symptoms, age, medical fitness, and the patient’s priorities; no single treatment is best for everyone.

As an Amazon Associate I earn from qualifying purchases.
What SRS does—and what it does not do
SRS delivers a highly focused radiation dose to the tumor in one session or a small number of sessions. The aim is long-term tumor control by stopping further growth, not physically removing the schwannoma. Because the tumor remains in place, SRS does not immediately relieve pressure on the brainstem or fourth ventricle. A patient with dangerous mass effect therefore cannot usually substitute SRS for decompressive surgery.
Crashes, No Sound, or Screen Glitches?
Random freezes, missing sound and display glitches usually trace back to one bad driver. Find and replace yours safely.Free scan · under a minutePC Slower Than It Used to Be?
A free scan shows the junk files, broken settings and background clutter dragging Windows down - then fixes them in one click.Free scan · Windows 10 & 11The treatment is planned from high-resolution MRI and is usually less disruptive than an operation, but it creates a need for long-term MRI and hearing surveillance. Tumor enlargement soon after treatment can represent temporary treatment-related swelling (pseudoprogression), so an early increase does not automatically mean that SRS failed.
#1 Best Overall

- [Ultra-Lightweight Ear Buds Designed for Small Ears] Each earbud weighs only 3.7g and features a compact, ergonomic in-ear design made especially for small ears. Secure, low-profile, and comfortable for workouts, all-day wear or overnight sleeping.The ultra-slim profile sits flush in your ear with no hard edges poking or rubbing, so you can even sleep on your side without discomfort.
- [Immersive Stereo Sound with TOZO OrigX Technology] TOZO OrigX tuning delivers clear vocals, balanced mids, and natural stereo sound for music, podcasts, and videos.
- [Long Battery Life for Daily Use] Get up to 7 hours of playtime on a single charge, with up to 32 hours total using the charging case—ideal for workdays, commuting, and extended listening sessions.
- [Bluetooth 5.3 & Stable Connection] Bluetooth 5.3 provides fast pairing, stable wireless performance, and reduced dropouts as you move around home or office.
- [Deep Bass with Clear Vocals] High-performance drivers produce punchy bass while keeping vocals clean and detailed for everyday listening.
How specialists decide whether a tumor is an SRS candidate
Tumor size and Koos stage
The International Stereotactic Radiosurgery Society (ISRS) considers Koos I–III tumors without significant mass effect good candidates for radiosurgery. In broad terms, Koos I is confined to the internal auditory canal; Koos II extends into the cerebellopontine-angle cistern without reaching the brainstem; Koos III reaches the brainstem without substantial compression; and Koos IV produces clear brainstem or fourth-ventricle displacement. The exact measurement and anatomy on the patient’s MRI matter more than a label alone.
| Tumor situation | How SRS is usually viewed | Typical management discussion |
|---|---|---|
| Intracanalicular or small (<2 cm), stable, no tinnitus or disabling symptoms | Observation is usually favored when hearing and cranial-nerve function are normal. | Serial MRI and hearing tests; SRS remains an alternative if growth appears or priorities change. |
| Small-to-moderate, growing Koos I–III without major brainstem compression | Common SRS indication. | Compare SRS with continued observation and microsurgery, considering hearing and symptom goals. |
| Koos III with limited contact but no symptomatic mass effect | Often suitable after multidisciplinary review. | Confirm that the fourth ventricle is not significantly deviated and that symptoms are not caused by dangerous pressure. |
| Koos IV or large tumor with symptomatic brainstem compression, hydrocephalus, or severe mass effect | Usually not an SRS-first situation. | Microsurgical decompression is generally needed; postoperative radiation may be considered in selected circumstances rather than primary SRS. |
| Large (maximum diameter at least 2.5 cm) without symptomatic mass effect | Selected cases may still be considered for SRS. | Suitability depends on hearing, symptoms, comorbidities, surgical risk, anatomy, and a strong preference to avoid resection. |
Documented growth is the most important trigger
For a newly discovered small tumor, a period of observation establishes whether it is actually enlarging. Growth on serial MRI is the principal reason to move from surveillance to active treatment. A growing Koos I–III tumor without significant compression is a typical SRS discussion. A growing Koos IV tumor with mass effect generally requires surgery because simply stopping growth does not remove the existing danger.
A single MRI difference is not enough to make the decision. Imaging should be compared using consistent technique and interpreted alongside symptoms, because measurement variation and short-term swelling can mimic progression. The treating team should define what amount and pattern of change would trigger intervention.
Symptoms, hearing, and cranial-nerve function
Hearing level, tinnitus, vertigo or imbalance, facial movement, and trigeminal sensation all influence the recommendation. For a small symptomatic tumor with impaired but useful hearing, the European Association of Neuro-Oncology (EANO) guideline notes that SRS may provide better hearing preservation and a lower facial-paresis risk than surgery, although the evidence quality is limited. That is a comparative possibility, not a promise for an individual patient.
Rank #2

- 【IP68 Waterproof Multifunctinal Smart Watch】Torjalph fitness activity tracker smart watch is IP68 waterproof technology ,you can wear it when swimming,handwashing,it's rain-proof which means that you perform multiple exercise modes outside without worrying about sweat or rain corroding your fitness smart watch,and this watch equipped with a 230 mAh large capacity battery magnetic charging ,and this sports activity tracker watch can be used 5-7 days If fully charged.
- 【Larger 1.83'' Full Screen Watch & Multi-dial Selection】1.83 inch full HD color touch screen smart watch for men / women provides excellent 240*284 resolution image quality ,This Bluetooth smart watch offers a better touch experience and remarkable immersion and ,more than 200 watch faces for you to choose from App"Da Fit ", you can change the dial style according to your mood to wear keeping the world on your wrist
- 【Accurate Activity Tracker Smart Watch 】sports watch activity tracker uses sweat and dust resistant breathable silicone strap, our Fitness Tracker Smart Watch for Android iOS Phones supports 12 sports modes,walking,running,bicycle,swimming,badminton,basketball,football,rope skipping. This bluetooth calls smart watch for men women is lightweight and stylish, bringing more convenient and relaxing sports experience while also providing more protection.
- 【Your 24 Hour Personal Daily Health Monitor】Fitness watch for women men full touch screen IP67 waterproof bluetooth smartwatch for Android iOS Phones with heart rate blood pressure monitor multifunction Andriod smart watch with steps counter sleep monitor sports fitness watch, monitoring blood oxygen saturation allows you to understand your physical condition in real time to track fitness progress ,to know your health status in time.
- 【More Functions Bluetooth Call Smart Watch】This fitness activity smart watch full screen for iPhone and Android phones includes a bunch of new features including:The bluetooth smart watch can hang up the phone, receive and display WhatsAPP /Text /Facebook /Twitter /Messenger reminder.Support sedentary reminder, alarm clock, stopwatch, timer,weather information,music control, remote camera control compatible with Android 5.0 and above or iOS 9.0 and above smartphones.
Normal facial and trigeminal function makes a less invasive strategy more attractive, while disabling imbalance, progressive facial weakness, loss of corneal sensation, or symptoms from pressure can shift the balance toward surgery. Tinnitus alone does not establish that SRS will eliminate the sound; treatment is intended primarily for tumor control, and tinnitus may persist or have another cause.
When observation is safer than immediate SRS
EANO describes observation as the management of choice for an incidental, asymptomatic vestibular schwannoma when cranial-nerve function is normal. The CNS guideline specifically recommends observation when an intracanalicular tumor or a small tumor under 2 cm has no tinnitus and no radiographic progression. The 2025 CNS update states that SRS should not be considered superior to observation alone for hearing preservation in this group.
Observation is an active plan rather than neglect. It requires the MRI and audiology schedule set by the treating team, review of any new hearing or balance change, and a predefined threshold for treatment. Choosing surveillance avoids radiation and surgery while the tumor is stable, but it also accepts the possibility that later growth could reduce hearing or make treatment more complicated.
SRS versus microsurgery: the trade-offs that matter
| Decision factor | SRS | Microsurgery |
|---|---|---|
| Primary purpose | Stops or controls further growth while leaving the tumor in place. | Removes all or part of the tumor and can decompress the brainstem immediately. |
| Best anatomic setting | Small-to-moderate tumors without major mass effect; selected larger tumors without symptomatic compression. | Large tumors with brainstem compression, fourth-ventricle deviation, hydrocephalus, or disabling pressure symptoms. |
| Hearing | Useful hearing may be preserved, but results depend on baseline hearing, dose, tumor anatomy, and follow-up duration. | Hearing preservation is possible in selected small tumors but may carry greater operative risk. |
| Facial nerve | For small symptomatic tumors, guidelines describe a potentially lower facial-paresis risk than surgery; individual risk varies. | Provides direct access but exposes the facial nerve to operative manipulation. |
| Relief of mass effect | Not immediate; the tumor remains and may transiently swell. | Rapid decompression when anatomy and symptoms require it. |
| Follow-up | Long-term MRI, hearing assessment, and neurologic examinations remain necessary. | Follow-up is also required for residual or recurrent tumor and postoperative function. |
| Evidence certainty | There is no randomized trial establishing one universal choice. Much of the comparative evidence is retrospective, so counseling must avoid guaranteed outcomes. | |
The practical question is not whether SRS is universally “better” than surgery. It is whether the expected benefit of durable control with less immediate disruption outweighs the fact that SRS cannot decompress a dangerous tumor and may not preserve hearing or resolve symptoms.
Rank #3
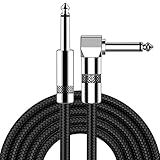
- [Low Noise High Fidelity] New bee guitar cord with 22AWG oxygen-free-copper center conductors provides enhanced signal transfer, the PVC insulation material and the high-density stranded copper double shield provide noise rejection for quiet operation
- [Ideal for Choice] New bee 1/4 straight and right angle metal connectors, ensures a secure connection in any instrument, pedal, or amp jack. L shape great fro on stage guitar stands
- [Wide Compatible] Suitable for mixer, power amplifier, microphone, effector, decoder, equalizer, electoronic organ, electric guitar, electric bass and other electronic equipments. Widely used in the installation of smart home, karaoke speaker, professional stage audio, etc
- [Easy Disassemble] Making incidental repairs quick and easy! Very nice, flexible cable
- [Dont Hesite to Order] 24 hours customer services and professional technology team are standing by
What hearing-preservation figures really mean
The 2017 ISRS guideline reported five-year hearing preservation of 41–79% in large contemporary single-fraction series using marginal doses of 12–14 Gy. This is a range across studies, not a personal forecast. Baseline speech discrimination, the definition of “serviceable” hearing, tumor size, cochlear dose, age, and the length and completeness of follow-up all affect the result.
An ISRS evidence summary published in 2024 estimated approximately 50–66% hearing preservation after SRS for intracanalicular tumors. That estimate also depends on baseline hearing and follow-up duration. Hearing can decline gradually even when the tumor is controlled, so a normal post-treatment MRI does not guarantee that hearing will remain unchanged.
For a patient whose primary goal is hearing preservation, the comparison should include continued observation, SRS, and hearing-preservation microsurgery where technically appropriate. Ask the team to state the hearing category being used, the patient’s starting audiogram, and how hearing will be managed if it worsens.
Do these 3 things before closing this tab:
1Clear out junk files and repair common Windows errors2Fix the driver behind crashes, sound loss and screen glitches3Repair Windows errors before they cause bigger problemsLarge tumors: when SRS may still be discussed
Size alone does not make SRS impossible, but the margin for error is smaller. For a tumor at least 2.5 cm in maximum diameter or classified as Koos IV, ideal SRS candidates in the ISRS guidance generally have no symptomatic mass effect or disabling symptoms, useful hearing, medical conditions that make resection unusually risky, or a strong preference to avoid surgery. The MRI must show enough space around the brainstem and fourth ventricle to deliver a safe plan.
Rank #4

- Digital Family Calendar: BSIMB digital calendar wall touch screen puts an end to your chaotic life. Designed for busy families, the digital calendar keeps you organised and in step with your family. Assign different colours and tasks to each family member to make family scheduling easier and more intuitive.
- Easy Setup and Auto-Sync: Plug in, connect to WLAN and auto-syn your electric calendar in minutes. Digital wall calendar compatible with Google calendar, iCloud calendar, Outlook calendar, Cozi calendar and Yahoo calendar. Add events directly on the device or through the ecalendar app. Electronic calendar stays current whether you're at work or traveling—no manual updates needed.
- All-In-One Home Assistant: Smart calendar builds habits and encourage independence with personalised chores. Display daily meal plan to reduce the daily ‘What's for dinner?’ stress. To-do lists keep track of everything you want. Turning chores into valuable achievements with stars and rewards, making life easier and more enjoyable.
- Manage Anytime Anywhere: BSIMB electronic calendar for family stay connected with the powerful ecalendar app. Access and manage your digital wall calendar anytime, anywhere with free features like stars & rewards, photo screensaver, chore charts, meals plans, to-do lists etc. Electronic planner paid features like Magic Import tailor advanced tools for users with special needs.
- Stay in Touch with Loved Ones: Share photos or videos from your phone to electronic wall calendar with app, instantly update your life moment, and keep in touch with your family, especially those who are far away; you can also surprise your smart calendar digital wall by sending him a wish card; it's also great for keeping tech-illiterate elders in touch with the youngsters.
If a large tumor is already causing hydrocephalus, marked brainstem compression, severe gait disturbance, or other pressure-related neurologic deficits, SRS is usually inadequate as the first treatment. A multidisciplinary team may discuss staged surgery, subtotal removal followed by radiation, or other individualized strategies, but those are not interchangeable with straightforward SRS for a small tumor.
Independent reader supportYour contribution helps us test, update, and keep practical guides available for everyone.How treatment is planned
- Confirm the diagnosis and anatomy. Planning uses thin-slice, volumetric, contrast-enhanced MRI together with T2-weighted imaging. The scans define the tumor, cochlea, brainstem, fourth ventricle, and cranial nerves as far as they can be visualized.
- Document function before treatment. Obtain formal audiology and examinations of facial movement, trigeminal sensation, eye protection, balance, and other relevant neurologic functions.
- Review the case as a team. ISRS recommends a multidisciplinary group including radiation oncology, neurosurgery, radiation physics, and radiation-therapy professionals with quality assurance. The team should review whether observation or decompression is safer before selecting SRS.
- Select the dose and delivery approach. Contemporary single-fraction practice commonly uses an 11–14 Gy marginal-dose range. The 2023 ISRS guidance associates 11–13 Gy with optimal local control for large tumors, but characterizes that evidence as class C; dose selection is individualized to tumor size, anatomy, and nearby structures.
- Agree on success and failure criteria. Before treatment, clarify how MRI changes will be interpreted, how long pseudoprogression may be watched, and what findings would lead to repeat SRS, surgery, or continued observation.
Follow-up after SRS
Follow-up should combine serial brain MRI, formal audiology, and neurologic examinations of facial and trigeminal function and balance. The schedule is individualized, but the need for surveillance is long term because control is assessed over time rather than immediately after the radiation session.
ISRS notes that enlargement during the first three years can be pseudoprogression. If the patient is neurologically stable and the imaging pattern is compatible with treatment effect, clinicians generally observe rather than label treatment failure immediately. New or worsening neurologic symptoms, sustained enlargement beyond the expected window, or unequivocal progression requires prompt specialist review.
Applying the criteria to common situations
Incidental 1.2-cm tumor, normal hearing, no symptoms, no growth
Observation is usually the first choice. SRS can be reconsidered if growth appears, hearing or balance changes, or the patient’s preferences change after counseling about surveillance and treatment risks.
1.8-cm tumor with documented growth and useful hearing
This is a classic SRS discussion if there is no significant brainstem compression. The decision should compare the hearing outlook with continued observation and with hearing-preservation surgery, rather than treating the measurement alone.
2.8-cm tumor, useful hearing, no mass effect, high operative risk
Selected SRS may be reasonable after review by neurosurgery and radiation specialists. The team must confirm that the tumor’s geometry permits safe dosing and that there is no hidden hydrocephalus or symptomatic compression.
Large Koos IV tumor with brainstem compression and worsening gait
Microsurgical decompression is generally favored because the urgent problem is pressure, not merely future growth. SRS alone would leave the mass in place and would not provide the needed immediate relief.
The Tool Desk
Outbyte Driver Updater FREEScan for outdated or missing drivers - takes under a minuteDriver Scan →Outbyte PC Repair FREEClear out junk files and repair common Windows errorsFree Scan →Questions to take to the specialist visit
- Has growth been demonstrated on comparable MRI scans, and what measurement threshold matters?
- What is the Koos grade, maximum diameter, and relationship to the brainstem and fourth ventricle?
- Is my hearing classified as serviceable, and what hearing endpoint will be used after treatment?
- What are the realistic options of observation, SRS, microsurgery, or a combined approach for my anatomy?
- If the tumor enlarges during the first three years after SRS, how will pseudoprogression be distinguished from failure?
- What symptoms should prompt an earlier MRI or neurologic assessment?
- Which specialists will participate in planning, and what is the proposed dose and quality-assurance process?
How certain is the evidence?
Recommendations are based largely on retrospective series, institutional experience, and guideline consensus rather than randomized trials comparing every option. The ISRS, EANO, and CNS guidance therefore support individualized counseling instead of a universal treatment rule. A recommendation for SRS means that the expected balance is favorable for that patient’s tumor and goals; it does not guarantee tumor control, hearing preservation, or freedom from later treatment.
Quick Recap
Product prices and availability are accurate as of the date/time indicated and are subject to change. Any price and availability information displayed on Amazon at the time of purchase will apply.

