Recommended Free Tools
A vaccine result is easiest to misread when you look at a single percentage. Start with the number of people who had the outcome in each study group, then examine the relative effect, the absolute difference, and the confidence interval. Only after that should you ask whether the study design, population, outcome definition and follow-up make the estimate applicable to you.
This approach explains why a “50% reduction” can mean 10 fewer cases per 1,000 people in one setting but 100 fewer in another, and why a confidence interval that crosses 1.0 does not prove that a vaccine has no benefit.

As an Amazon Associate I earn from qualifying purchases.
What to check before reading any percentage
A risk estimate has meaning only in the setting in which it was measured. Before interpreting a vaccine result, identify five features of the study:
Crashes, No Sound, or Screen Glitches?
Random freezes, missing sound and display glitches usually trace back to one bad driver. Find and replace yours safely.Free scan · under a minuteWindows Errors? Fix Them Before They Spread
Repair common Windows errors and clear accumulated junk for a smoother, more stable PC - no reinstall needed.Free scan · no reinstall- Design: Was it a randomized trial or an observational study in routine practice?
- Population: Which ages, health conditions, vaccination histories and geographic settings were included?
- Outcome: Was the endpoint infection, symptomatic disease, laboratory-confirmed disease, hospitalization, death or something else?
- Comparator: Were vaccinated participants compared with placebo recipients, unvaccinated people, or another vaccine or schedule?
- Follow-up: Over what period after vaccination were events counted?
The same vaccine can have different estimates when the circulating variant, dose schedule, prior immunity, outcome definition or follow-up period changes. A percentage without these details is not portable evidence.
#1 Best Overall

- [Ultra-Lightweight Ear Buds Designed for Small Ears] Each earbud weighs only 3.7g and features a compact, ergonomic in-ear design made especially for small ears. Secure, low-profile, and comfortable for workouts, all-day wear or overnight sleeping.The ultra-slim profile sits flush in your ear with no hard edges poking or rubbing, so you can even sleep on your side without discomfort.
- [Immersive Stereo Sound with TOZO OrigX Technology] TOZO OrigX tuning delivers clear vocals, balanced mids, and natural stereo sound for music, podcasts, and videos.
- [Long Battery Life for Daily Use] Get up to 7 hours of playtime on a single charge, with up to 32 hours total using the charging case—ideal for workdays, commuting, and extended listening sessions.
- [Bluetooth 5.3 & Stable Connection] Bluetooth 5.3 provides fast pairing, stable wireless performance, and reduced dropouts as you move around home or office.
- [Deep Bass with Clear Vocals] High-performance drivers produce punchy bass while keeping vocals clean and detailed for everyday listening.
Read the absolute risks first
Absolute risk is the proportion of people in a group who experienced the specified outcome during the study period. If 10 of 1,000 vaccinated participants developed the outcome, the vaccinated risk is 10/1,000, or 1%. If 20 of 1,000 unvaccinated participants developed it, the unvaccinated risk is 20/1,000, or 2%.
These counts answer the practical question: how many people had the outcome in each group? They also show the baseline risk against which any relative percentage must be judged.
Absolute risk difference
The absolute risk difference is the subtraction of the two risks:
Quick wins for a faster PC:
Fix the driver behind crashes, sound loss and screen glitchesFind Drivers →Clear out junk files and repair common Windows errorsFree Scan →Scan for outdated or missing drivers - takes under a minuteDriver Scan →absolute risk difference = risk in vaccinated group − risk in comparison group
For a beneficial vaccine outcome, writers often express the absolute risk reduction as comparison-group risk minus vaccinated-group risk. In the example above, 2% − 1% equals a 1-percentage-point reduction, or 10 fewer cases per 1,000 people.
Use the unit stated by the study. “One percentage point” is not the same as “one percent.” A change from 2% to 1% is a one-percentage-point decrease and a 50% relative reduction.
Why baseline risk changes the practical benefit
Imagine the same relative effect is applied to two different starting risks. A comparison group with a 2% risk and a vaccinated group with a 1% risk produces 10 fewer cases per 1,000. If the comparison-group risk is 20% and the vaccinated risk is 10%, the relative risk is still 0.50, but the absolute reduction is 10 percentage points, or 100 fewer cases per 1,000.
What’s actually slowing this PC down?
Pick the symptom - the matching free tool is one click away.
| Comparison-group risk | Vaccinated risk | Relative risk | Relative reduction | Absolute reduction | Fewer cases per 1,000 |
|---|---|---|---|---|---|
| 2% | 1% | 0.50 | 50% | 1 percentage point | 10 |
| 20% | 10% | 0.50 | 50% | 10 percentage points | 100 |
The relative result is identical, but the number of cases avoided is ten times larger in the higher-risk setting. That is why relative and absolute effects belong together, as recommended by the CONSORT Group.
Rank #2

- 【IP68 Waterproof Multifunctinal Smart Watch】Torjalph fitness activity tracker smart watch is IP68 waterproof technology ,you can wear it when swimming,handwashing,it's rain-proof which means that you perform multiple exercise modes outside without worrying about sweat or rain corroding your fitness smart watch,and this watch equipped with a 230 mAh large capacity battery magnetic charging ,and this sports activity tracker watch can be used 5-7 days If fully charged.
- 【Larger 1.83'' Full Screen Watch & Multi-dial Selection】1.83 inch full HD color touch screen smart watch for men / women provides excellent 240*284 resolution image quality ,This Bluetooth smart watch offers a better touch experience and remarkable immersion and ,more than 200 watch faces for you to choose from App"Da Fit ", you can change the dial style according to your mood to wear keeping the world on your wrist
- 【Accurate Activity Tracker Smart Watch 】sports watch activity tracker uses sweat and dust resistant breathable silicone strap, our Fitness Tracker Smart Watch for Android iOS Phones supports 12 sports modes,walking,running,bicycle,swimming,badminton,basketball,football,rope skipping. This bluetooth calls smart watch for men women is lightweight and stylish, bringing more convenient and relaxing sports experience while also providing more protection.
- 【Your 24 Hour Personal Daily Health Monitor】Fitness watch for women men full touch screen IP67 waterproof bluetooth smartwatch for Android iOS Phones with heart rate blood pressure monitor multifunction Andriod smart watch with steps counter sleep monitor sports fitness watch, monitoring blood oxygen saturation allows you to understand your physical condition in real time to track fitness progress ,to know your health status in time.
- 【More Functions Bluetooth Call Smart Watch】This fitness activity smart watch full screen for iPhone and Android phones includes a bunch of new features including:The bluetooth smart watch can hang up the phone, receive and display WhatsAPP /Text /Facebook /Twitter /Messenger reminder.Support sedentary reminder, alarm clock, stopwatch, timer,weather information,music control, remote camera control compatible with Android 5.0 and above or iOS 9.0 and above smartphones.
Relative risk: what the ratio means
Relative risk (RR) compares the risk in the vaccinated or otherwise exposed group with the risk in the unvaccinated or unexposed group:
RR = risk in vaccinated group ÷ risk in comparison group
- RR = 1.0: the observed risks are equal.
- RR below 1.0: the vaccinated group had lower observed risk.
- RR above 1.0: the vaccinated group had higher observed risk.
For the 1% versus 2% example, RR = 0.01 ÷ 0.02 = 0.50. A relative risk of 0.50 corresponds to a relative risk reduction of 50%, calculated as (1 − RR) × 100%, when the outcome is undesirable and the vaccine is associated with lower risk.
Do these 3 things before closing this tab:
1Clear out junk files and repair common Windows errors2Fix the driver behind crashes, sound loss and screen glitches3Repair Windows errors before they cause bigger problemsRelative risk is not a percentage of people protected
An RR of 0.50 does not mean that half of all vaccinated people are protected, nor that half of infections in every population will be prevented. It describes the ratio of two event risks under the study’s particular conditions. The absolute event counts and baseline risk tell you how many cases that ratio represents.
When a ratio is difficult to use
If events are very rare, small changes in counts can produce an apparently large relative effect. Conversely, when baseline risk is high, a modest relative effect can translate into many prevented cases. The Advisory Committee on Immunization Practices cautions that when baseline risk is very low, pooled relative-effect intervals can mislead; pooled risk differences may be more informative.
Confidence intervals: the uncertainty around an estimate
A point estimate is the study’s best single summary, such as RR 0.70. A 95% confidence interval (CI) gives a range of values compatible with the data under the study’s statistical analysis model. The CDC Field Epidemiology Manual describes it this way: “A CI can be regarded as the range of values consistent with the data in a study.”
The interval reflects sampling uncertainty. It does not by itself correct for biased recruitment, inaccurate outcome measurement, unmeasured confounding or a mismatch between the study population and the population you care about.
Locate the null value
For a relative risk, the null value is 1.0 because a ratio of one means equal risk. Compare the entire interval with 1.0:
Rank #3
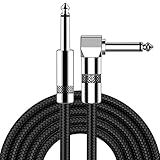
- [Low Noise High Fidelity] New bee guitar cord with 22AWG oxygen-free-copper center conductors provides enhanced signal transfer, the PVC insulation material and the high-density stranded copper double shield provide noise rejection for quiet operation
- [Ideal for Choice] New bee 1/4 straight and right angle metal connectors, ensures a secure connection in any instrument, pedal, or amp jack. L shape great fro on stage guitar stands
- [Wide Compatible] Suitable for mixer, power amplifier, microphone, effector, decoder, equalizer, electoronic organ, electric guitar, electric bass and other electronic equipments. Widely used in the installation of smart home, karaoke speaker, professional stage audio, etc
- [Easy Disassemble] Making incidental repairs quick and easy! Very nice, flexible cable
- [Dont Hesite to Order] 24 hours customer services and professional technology team are standing by
- An interval wholly below 1.0 is compatible with a lower risk in the vaccinated group at that confidence level.
- An interval wholly above 1.0 is compatible with a higher risk.
- An interval that crosses 1.0 is compatible with no difference as well as effects in either direction allowed by its limits.
For an absolute risk difference, the null value is 0 percentage points. The same crossing rule applies, but you compare the interval with zero rather than one.
Worked confidence-interval examples
An RR of 0.70 with a 95% CI of 0.55–0.90 is entirely below 1.0. The data are compatible with a protective association, with plausible relative risks ranging from 0.55 to 0.90 under the model.
An RR of 0.70 with a 95% CI of 0.40–1.20 crosses 1.0. The data are compatible with anything from a larger protective effect to a possible increase in risk. At that confidence level, the study does not establish an effect statistically distinguishable from no difference. “Not significant” does not necessarily mean “no association,” as the CDC notes; the interval may simply be too wide to exclude important benefit or harm.
What “95%” does and does not mean
A 95% CI is not a statement that there is a 95% probability that the true effect lies inside this particular interval. In the frequentist framework used for these intervals, the method would capture the fixed underlying value in about 95% of repeated samples if its assumptions held. For a reader, the practical interpretation is the set of effect sizes reasonably compatible with the observed data and model, not a guarantee about the true value.
Narrow versus wide intervals
A narrow CI indicates a more precise estimate, often because the study has more events or less statistical variability. A wide CI indicates substantial uncertainty. Precision is not validity: a large, tightly estimated observational study can still be biased if vaccinated and unvaccinated participants differ in ways the analysis did not adequately handle.
From relative risk to vaccine efficacy or effectiveness
In a randomized trial, vaccine efficacy is often summarized as:
VE = (1 − RR) × 100%
The formula is meaningful only when the outcome, follow-up period, comparator, and analysis population are specified. “Efficacy” generally refers to performance under trial conditions; “effectiveness” describes performance in routine practice, where vaccination choices, access, behavior and health status can differ.
A trial example with its full context
A CDC Advisory Committee on Immunization Practices evidence review of a Moderna COVID-19 vaccine randomized-trial result reported lower risk of symptomatic laboratory-confirmed COVID-19 with vaccination: RR 0.07, 95% CI 0.05–0.09. The review calculated absolute risk from the placebo-group risk. That estimate belongs to the trial’s participants, schedule, outcome definition and follow-up; it should not be transplanted to another variant, dose schedule, outcome or population.
Rank #4

- Digital Family Calendar: BSIMB digital calendar wall touch screen puts an end to your chaotic life. Designed for busy families, the digital calendar keeps you organised and in step with your family. Assign different colours and tasks to each family member to make family scheduling easier and more intuitive.
- Easy Setup and Auto-Sync: Plug in, connect to WLAN and auto-syn your electric calendar in minutes. Digital wall calendar compatible with Google calendar, iCloud calendar, Outlook calendar, Cozi calendar and Yahoo calendar. Add events directly on the device or through the ecalendar app. Electronic calendar stays current whether you're at work or traveling—no manual updates needed.
- All-In-One Home Assistant: Smart calendar builds habits and encourage independence with personalised chores. Display daily meal plan to reduce the daily ‘What's for dinner?’ stress. To-do lists keep track of everything you want. Turning chores into valuable achievements with stars and rewards, making life easier and more enjoyable.
- Manage Anytime Anywhere: BSIMB electronic calendar for family stay connected with the powerful ecalendar app. Access and manage your digital wall calendar anytime, anywhere with free features like stars & rewards, photo screensaver, chore charts, meals plans, to-do lists etc. Electronic planner paid features like Magic Import tailor advanced tools for users with special needs.
- Stay in Touch with Loved Ones: Share photos or videos from your phone to electronic wall calendar with app, instantly update your life moment, and keep in touch with your family, especially those who are far away; you can also surprise your smart calendar digital wall by sending him a wish card; it's also great for keeping tech-illiterate elders in touch with the youngsters.
To turn that RR into an absolute benefit, you need the comparison-group event risk from the same analysis. Without that baseline, the relative estimate alone cannot tell you how many cases were prevented.
Randomized trials and observational effectiveness studies
Randomized trials
Randomized allocation is intended to balance known and unknown characteristics between groups at the start of a trial. A placebo or other control provides a defined comparator, and prespecified follow-up and outcome rules can make the contrast easier to interpret. Even so, examine exclusions, loss to follow-up, outcome definitions and whether the reported analysis follows everyone as randomized (intention-to-treat) or includes only participants who adhered to the protocol (per-protocol).
Observational studies
In an observational effectiveness study, people receive or decline vaccination in routine practice rather than being assigned by investigators. Vaccinated participants may differ from unvaccinated participants in age, medical care, health conditions, behavior, occupation, prior infection or likelihood of testing. These differences can confound the association if they are related to both vaccination and the outcome.
Free tools Windows power users keep installed
One-click scans. No signup required.
Adjustment methods can reduce measured differences, but they cannot guarantee that all relevant factors were measured correctly. Read the eligibility criteria, calendar period, exposure definition, outcome ascertainment, missing-data handling and adjustment variables before treating an observational estimate as causal.
A repeatable method for reading any vaccine result
- Write down the question. Identify the exact outcome, such as symptomatic laboratory-confirmed disease, hospitalization or infection, and the time period.
- Identify both groups. Record who was vaccinated, who was the comparator, the dose or schedule, and when exposure status was determined.
- Calculate or locate event risks. Note the number of events and the number of people at risk in each group. Convert them to percentages or cases per 1,000.
- Read the absolute difference. Subtract the risks and keep the unit—percentage points or cases per 1,000.
- Read the relative measure. Check whether the paper reports RR, a hazard ratio, an odds ratio or VE. Do not treat these measures as interchangeable without understanding the analysis.
- Inspect the confidence interval. For RR, compare it with 1.0; for a risk difference, compare it with zero. Note its width, not just whether it crosses the null.
- Check the design and bias risks. Look for randomization, missing data, differential testing, confounding and deviations from the assigned schedule.
- Test applicability. Ask whether the participants, circulating pathogen, vaccine product, schedule, prior immunity and follow-up resemble the situation you are evaluating.
How to compare two vaccine estimates fairly
Comparing two percentages from different papers can create a false ranking. Use the same comparison axes before drawing a conclusion.
| Question | Why it matters |
|---|---|
| Is the outcome defined the same way? | Infection, symptomatic disease, hospitalization and death are different endpoints. |
| Is the follow-up period the same? | Protection can vary with time since vaccination and changing exposure. |
| Are the populations comparable? | Age, health status, prior infection and exposure intensity change baseline risk. |
| Is the comparator equivalent? | Placebo, unvaccinated people and another vaccine do not represent the same contrast. |
| Are the absolute event rates shown? | They reveal the practical number of cases associated with the relative estimate. |
| How do the intervals compare? | Width indicates precision; position relative to the null indicates compatibility with no difference. |
| Are design and bias risks similar? | A randomized estimate and an adjusted observational estimate answer related but not identical questions. |
| Is the result direct or extrapolated? | Applying an estimate to another variant, schedule or population may not be justified. |
If one study reports only VE and another reports only an absolute risk difference, you cannot decide which vaccine is “better” from those figures alone. Find the underlying event rates and matching outcome and follow-up definitions.
Common traps and how to avoid them
“50% effective” sounds like half the people are protected
Usually it means the estimated risk in the vaccinated group was half the comparison-group risk for a defined outcome and period. Convert it to cases per 1,000 using the comparison-group risk.
A confidence interval crossing 1.0 proves the vaccine does nothing
It does not. Such an interval is compatible with no difference, but also with effects in either direction within its limits. A wide interval may reflect few events or limited sample size.
A narrow interval proves the result is trustworthy
It proves only that the estimate is precise under the model. Systematic bias, confounding or poor outcome ascertainment can remain tightly estimated.
Statistical significance is treated as clinical importance
A tiny absolute difference can be statistically distinguishable from zero in a very large study, while a potentially important benefit can fail to reach conventional significance in a small study. Report both the size of the effect and its uncertainty.
Percentages from different outcomes are compared directly
A result for infection cannot be placed beside a result for hospitalization as though they measured the same thing. Match outcome, population, comparator and follow-up first.
The Tool Desk
Outbyte PC Repair FREERepair Windows errors before they cause bigger problemsFix Now →Outbyte Driver Updater FREEScan for outdated or missing drivers - takes under a minuteDriver Scan →Trial efficacy is presented as a current real-world guarantee
Trial conditions may differ from routine practice, and protection estimates can change with variants, schedules and prior immunity. Keep the original context attached to every number.
What a complete vaccine result should report
A reader should be able to find, in one place:
- the number of participants and events in each group;
- the absolute risk in each group;
- the absolute risk difference or reduction;
- the relative measure and its 95% CI;
- the outcome definition and follow-up window;
- the population, setting and calendar period;
- the comparator and vaccination schedule;
- the analysis population, including intention-to-treat or per-protocol status;
- important missing-data, testing and loss-to-follow-up details; and
- the study design and major potential sources of bias.
CONSORT guidance recommends reporting both relative and absolute effects with confidence intervals because neither conveys the complete picture alone.
A compact example you can reproduce
Suppose a study follows 1,000 vaccinated and 1,000 unvaccinated people. Ten vaccinated participants and 20 unvaccinated participants develop the defined outcome.
- Vaccinated risk:
10 ÷ 1,000 = 0.01 = 1%. - Unvaccinated risk:
20 ÷ 1,000 = 0.02 = 2%. - Relative risk:
0.01 ÷ 0.02 = 0.50. - Relative risk reduction:
(1 − 0.50) × 100% = 50%. - Absolute risk reduction:
2% − 1% = 1 percentage point. - Cases avoided at this baseline:
10 per 1,000 people.
The correct plain-language reading is: during this study period and for this outcome, the vaccinated group had half the observed risk, corresponding to 10 fewer cases per 1,000 at the study’s comparison-group risk. It is not a promise that every population will experience the same percentage or number.
Questions to ask when the result affects a decision
- What outcome am I trying to prevent, and is that the outcome measured?
- What was the starting risk in the comparison group?
- How many events were actually observed?
- Does the confidence interval include effects that would matter to me?
- Could differences between groups explain part of the association?
- Does the study match my age, health status, location, exposure level and vaccination history?
- How long does the estimate apply after vaccination?
These questions turn a headline percentage into an evidence-based estimate of practical benefit and uncertainty.
Quick Recap
Product prices and availability are accurate as of the date/time indicated and are subject to change. Any price and availability information displayed on Amazon at the time of purchase will apply.

