Quick wins for a faster PC:
Repair Windows errors before they cause bigger problemsFix Now →Scan for outdated or missing drivers - takes under a minuteDriver Scan →The safest way to evaluate an AI medical scribe is to treat it as a clinical-documentation system, not a transcription shortcut. Define the visits, patients, languages, note formats, privacy obligations, and EHR workflow you actually need; test shortlisted tools on representative encounters; measure errors and editing time; verify data and contract controls; obtain appropriate patient consent; and require clinician review and approval before any generated note becomes part of the record.
What an AI medical scribe does—and what it does not do
An ambient AI scribe generally listens to a clinical conversation, creates a transcript, and produces a draft note in a selected format. Depending on the product, it may run inside an electronic health record (EHR), connect through an application programming interface (API), or operate as standalone software that requires a separate transfer or copy-and-paste step.

As an Amazon Associate I earn from qualifying purchases.
The output is a draft. It is not an independent clinical record, diagnosis, or decision-maker. The clinician must compare the draft with what was actually said, correct it, and authorize the final note. The American Psychological Association’s Guidance for the Evaluation of AI Scribes (December 2025) states: “You must review AI generated documentation for accuracy and edit as needed prior to signing and the documentation becoming part of the clinical record.” It also says that, while AI may assist with documentation, the clinician remains responsible for clinical decisions and documentation accuracy. The Australian Commission on Safety and Quality in Health Care makes the same allocation of responsibility in its August 2025 ambient-scribe safety scenario.
Free tools Windows power users keep installed
One-click scans. No signup required.
That distinction should shape procurement. A tool that saves keystrokes but introduces an unsupported medication, omits a safety instruction, assigns a statement to the wrong speaker, or makes approval difficult can increase risk rather than reduce workload.
#1 Best Overall

- [Ultra-Lightweight Ear Buds Designed for Small Ears] Each earbud weighs only 3.7g and features a compact, ergonomic in-ear design made especially for small ears. Secure, low-profile, and comfortable for workouts, all-day wear or overnight sleeping.The ultra-slim profile sits flush in your ear with no hard edges poking or rubbing, so you can even sleep on your side without discomfort.
- [Immersive Stereo Sound with TOZO OrigX Technology] TOZO OrigX tuning delivers clear vocals, balanced mids, and natural stereo sound for music, podcasts, and videos.
- [Long Battery Life for Daily Use] Get up to 7 hours of playtime on a single charge, with up to 32 hours total using the charging case—ideal for workdays, commuting, and extended listening sessions.
- [Bluetooth 5.3 & Stable Connection] Bluetooth 5.3 provides fast pairing, stable wireless performance, and reduced dropouts as you move around home or office.
- [Deep Bass with Clear Vocals] High-performance drivers produce punchy bass while keeping vocals clean and detailed for everyday listening.
1. Define the job before seeing a product demo
Write a short intended-use statement and a list of non-negotiable constraints. A generic demonstration cannot show whether a product fits your practice.
Describe the encounters and patients
- List each specialty and service line in scope. A primary-care follow-up, behavioral-health session, emergency visit, procedure note, and therapy encounter have different documentation requirements.
- Specify visit types: new-patient, follow-up, preventive, chronic-care, urgent, group, family or caregiver, and multi-clinician encounters.
- Include in-person, telephone, video, and hybrid visits. Confirm whether the tool can distinguish participants when several people speak.
- Document languages, dialects, accents, code-switching, interpreters, and common clinical abbreviations. Do not assume performance in one language predicts performance in another.
- Describe the patient population, including children, older adults, people with speech or hearing differences, and patients whose communication may be affected by illness or medication.
Specify the documentation standard
- Name the required note formats, such as SOAP, DAP, BIRP, narrative, consultation, procedure, discharge, or specialty-specific templates.
- Identify mandatory fields, structured data, diagnosis and procedure coding, medication reconciliation, risk assessments, follow-up instructions, and co-signature rules.
- State which sections may be drafted automatically and which require manual entry or a second clinician’s approval.
- Define customization needs: organization terminology, clinician preferences, macros, headings, problem-list conventions, and rules for separating reported history from clinical assessment.
Set a baseline for the problem you want to solve
Measure the current process before a pilot. Useful baselines include average documentation time after a visit, time spent correcting dictation, chart-completion delay, after-hours work, missing required fields, and clinician satisfaction. Without a baseline, a vendor’s claim that the tool is “faster” has no practice-specific meaning.
Also decide whether an ambient scribe is appropriate at all. Some visits may be too sensitive, too unpredictable, or too technically constrained for recording. A practice can limit use to defined visit types rather than making the tool mandatory for every encounter.
2. Establish accountability and local requirements
Assign responsibility before procurement. Name the clinical owner, privacy or compliance lead, information-security lead, EHR or IT owner, procurement contact, training lead, and person responsible for incident escalation. Decide who can approve a template, pause use for a visit type, or stop the pilot after a safety event.
Jurisdiction matters. Consent, recording, privacy, medical-record, device-regulation, and procurement requirements differ by country, state, province, and sometimes facility. The APA guide is preliminary and written for psychologists; practices in other specialties should adapt it. NHS England material, where consulted, applies to England, and Australian Commission guidance applies in the Australian context. None of these sources establishes a universal rule for every practice.
For a US practice, determine whether the vendor is acting as a business associate and whether a business associate agreement (BAA) is required. A vendor’s general statement that it is “HIPAA compliant” is not a substitute for reviewing your obligations, the actual contract, configuration, access controls, and data flows. Outside the United States, map the product to the privacy and health-record rules that apply locally and obtain jurisdiction-specific legal advice when needed.
Rank #2

- 【IP68 Waterproof Multifunctinal Smart Watch】Torjalph fitness activity tracker smart watch is IP68 waterproof technology ,you can wear it when swimming,handwashing,it's rain-proof which means that you perform multiple exercise modes outside without worrying about sweat or rain corroding your fitness smart watch,and this watch equipped with a 230 mAh large capacity battery magnetic charging ,and this sports activity tracker watch can be used 5-7 days If fully charged.
- 【Larger 1.83'' Full Screen Watch & Multi-dial Selection】1.83 inch full HD color touch screen smart watch for men / women provides excellent 240*284 resolution image quality ,This Bluetooth smart watch offers a better touch experience and remarkable immersion and ,more than 200 watch faces for you to choose from App"Da Fit ", you can change the dial style according to your mood to wear keeping the world on your wrist
- 【Accurate Activity Tracker Smart Watch 】sports watch activity tracker uses sweat and dust resistant breathable silicone strap, our Fitness Tracker Smart Watch for Android iOS Phones supports 12 sports modes,walking,running,bicycle,swimming,badminton,basketball,football,rope skipping. This bluetooth calls smart watch for men women is lightweight and stylish, bringing more convenient and relaxing sports experience while also providing more protection.
- 【Your 24 Hour Personal Daily Health Monitor】Fitness watch for women men full touch screen IP67 waterproof bluetooth smartwatch for Android iOS Phones with heart rate blood pressure monitor multifunction Andriod smart watch with steps counter sleep monitor sports fitness watch, monitoring blood oxygen saturation allows you to understand your physical condition in real time to track fitness progress ,to know your health status in time.
- 【More Functions Bluetooth Call Smart Watch】This fitness activity smart watch full screen for iPhone and Android phones includes a bunch of new features including:The bluetooth smart watch can hang up the phone, receive and display WhatsAPP /Text /Facebook /Twitter /Messenger reminder.Support sedentary reminder, alarm clock, stopwatch, timer,weather information,music control, remote camera control compatible with Android 5.0 and above or iOS 9.0 and above smartphones.
3. Demand product-specific evidence
Ask vendors for evidence about the exact product, model, language, workflow, and release you would use—not a general claim about artificial intelligence.
Questions about validation
- What population, specialties, visit modes, languages, and accents were included in testing?
- Were encounters real, de-identified, simulated, or vendor-authored? How closely did they resemble your documentation standard?
- How were omissions, unsupported additions, hallucinations, attribution errors, over-summarization, and note completeness measured?
- Were errors evaluated at the transcript level, the generated-note level, or both?
- How did clinicians review and grade the output, and were graders independent of the vendor?
- How are updates validated before release, and can your practice delay or test an update?
- What evidence exists for the languages, specialties, patient groups, and visit modes you plan to use?
A Mayo Clinic Proceedings: Digital Health evaluation published in 2025 assessed five platforms across 14 simulated ambulatory encounters and found variability in transcript and note quality. The study is useful evidence that platforms can differ, but its simulated design is not a performance estimate for your practice and cannot replace local validation.
Questions about limits
Require a written list of unsupported scenarios, known failure modes, minimum device or network requirements, and circumstances in which the vendor recommends not using the product. Ask how a user reports a suspected error, how quickly incidents are investigated, and whether the practice receives a meaningful release note when the model or workflow changes.
4. Run a structured, representative pilot
A pilot should resemble normal work, include difficult cases, and produce comparable measurements for every candidate. Do not allow a polished demo to substitute for hands-on testing.
- Choose the scope. Select the specialties, clinicians, visit types, languages, and EHR workflows you expect to use. Include in-person and telehealth encounters where relevant.
- Create a test set. Use consenting real encounters or carefully designed simulations that represent routine and high-risk documentation. Include interruptions, corrections, medication names, negations, numbers, multiple speakers, interpreters, and conversations that change direction.
- Define the reference. Have an experienced clinician establish what a correct note should contain, what must not be inferred, and which fields are mandatory. The reference is the comparison standard, not merely the vendor’s preferred template.
- Run each candidate under comparable conditions. Use the same encounter types, device setup, network conditions, note requirements, and review instructions. Record failures such as dropped audio or service interruptions.
- Have clinicians review drafts against the encounter. Require them to mark omissions, fabricated or unsupported details, incorrect speaker attribution, wrong negation, wrong dosage or timing, inappropriate certainty, and missing follow-up instructions.
- Measure editing and approval. Record time from draft availability to signed note, number and severity of edits, time spent checking the transcript, and whether the clinician can clearly see what was generated and what was changed.
- Check subgroup performance. Compare results by specialty, clinician, language, accent, age group, visit mode, and number of participants. A satisfactory average can hide a serious problem for one patient group.
- Set pass gates before seeing results. Define which errors are unacceptable, the maximum editing burden, required integration reliability, and the process for suspending use if a safety event occurs.
Metrics worth recording
| Measure | What to record | Why it matters |
|---|---|---|
| Omissions | Required facts, symptoms, medications, allergies, instructions, or plans missing from the draft | An incomplete note can misrepresent the encounter or leave follow-up actions undocumented |
| Unsupported additions | Details not stated or justified by the conversation | Invented findings, history, or plans can become clinical misinformation |
| Attribution and negation | Who said a statement and whether it was affirmed, denied, historical, or conditional | Speaker and meaning errors can reverse clinical intent |
| Completeness | Presence of mandatory sections and required structured fields | A readable note may still fail organizational or billing requirements |
| Editing burden | Minutes, keystrokes, number of corrections, and review of the source transcript | Time saved in typing is not useful if checking takes longer |
| Equity of performance | Results by language, accent, age, disability, specialty, and visit mode | Aggregate accuracy can conceal uneven risk |
| Reliability | Capture failures, latency, outages, duplicate notes, and integration errors | Workflow interruptions and missing records require a safe fallback |
| Patient experience | Questions, refusals, complaints, and whether patients felt heard | Recording must not undermine trust or access |
Grade errors by severity rather than counting them equally. A misspelled nonclinical word and an omitted allergy are not equivalent. Have clinicians review any error that could alter diagnosis, treatment, medication, risk assessment, consent, or follow-up.
5. Verify privacy, security, and data handling
Trace every category of session data: audio, transcript, generated note, corrections, metadata, user identifiers, device logs, and support records. Obtain answers in writing and reconcile them with the privacy policy, terms of service, security exhibits, BAA where applicable, and your configuration.
Rank #3
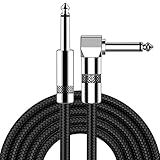
- [Low Noise High Fidelity] New bee guitar cord with 22AWG oxygen-free-copper center conductors provides enhanced signal transfer, the PVC insulation material and the high-density stranded copper double shield provide noise rejection for quiet operation
- [Ideal for Choice] New bee 1/4 straight and right angle metal connectors, ensures a secure connection in any instrument, pedal, or amp jack. L shape great fro on stage guitar stands
- [Wide Compatible] Suitable for mixer, power amplifier, microphone, effector, decoder, equalizer, electoronic organ, electric guitar, electric bass and other electronic equipments. Widely used in the installation of smart home, karaoke speaker, professional stage audio, etc
- [Easy Disassemble] Making incidental repairs quick and easy! Very nice, flexible cable
- [Dont Hesite to Order] 24 hours customer services and professional technology team are standing by
Data-lifecycle questions
| Stage | Questions to answer |
|---|---|
| Capture | What is recorded, when does recording start and stop, and can users verify that it has stopped? |
| Transmission | Is data encrypted in transit? Which devices, networks, and subprocessors receive it? |
| Processing | Which models process audio and text? Are third-party model providers involved, and are they covered by appropriate agreements? |
| Storage | Where are audio, transcripts, drafts, logs, and backups stored? Are they separated from the legal medical record? |
| Retention | How long is each data type retained, including backups and support copies? Can the practice set a shorter period? |
| Deletion | Who can delete data, how is deletion verified, and what remains in immutable backups? |
| Secondary use | Are data used for model training, quality improvement, analytics, advertising, or product development? Is opt-out or contractual prohibition available? |
| Access | Which vendor personnel can view data, under what approvals, and with what audit trail? |
Security controls to verify
- Encryption in transit and at rest, with documented key-management responsibilities.
- Role-based access, least privilege, multifactor authentication, session timeout, and administrator controls.
- Audit logs that your practice can review and retain.
- Independent security attestations or audits, penetration-testing practices, vulnerability disclosure, and breach-notification procedures.
- Subprocessor locations and responsibilities, including what happens when a subprocessor changes.
- Business-continuity, disaster-recovery, export, and termination procedures.
Do not assume that a product’s default settings match your policy. Configure retention, user access, recording indicators, and data sharing deliberately, then test that the settings work as documented.
6. Plan consent and patient communication
Patients should understand that an AI system is recording or processing the visit, what it creates, how the clinician reviews it, and what happens if they decline. Use language appropriate to the patient and the care setting rather than relying only on a dense privacy notice.
Elements of a practical explanation
- Identify the tool and the point at which recording or processing begins.
- Explain whether audio is retained, whether a transcript is created, and where the final note is stored.
- State that the clinician remains responsible for checking and signing the note.
- Offer a clear way to decline or withdraw consent where required or appropriate.
- Explain the alternative documentation process and ensure declining does not result in poorer access or treatment.
- Record consent, refusal, or withdrawal according to the rules that apply in your jurisdiction and organization.
Consent requirements vary. Some jurisdictions distinguish between one-party and all-party recording consent; others impose additional rules for health information, minors, telehealth, or cross-border processing. Verify the rules that govern each location in which the practice operates instead of importing a policy from another country.
Do these 3 things before closing this tab:
1Fix the driver behind crashes, sound loss and screen glitches2Clear out junk files and repair common Windows errors3Scan for outdated or missing drivers - takes under a minute7. Compare integration and workflow options
Integration determines whether a draft actually saves work. Test the complete path from opening a visit to signing the final record, including patient selection, template choice, corrections, co-signature, coding, attachments, and downtime.
| Deployment pattern | Potential advantages | Questions and risks |
|---|---|---|
| EHR-embedded | Fewer context switches; may place drafts and approval controls in the clinician’s normal workspace | Confirm supported EHR edition, templates, permissions, release dependencies, and how updates are tested |
| API-connected | Can connect systems while allowing a specialized user interface | Verify patient matching, authentication, data mapping, latency, error handling, and who supports the interface |
| Standalone | May be quicker to trial and usable across multiple systems | Copy-and-paste or manual upload can introduce wrong-patient risk, duplicate data, extra logins, and weaker auditability |
Workflow tests to perform
- Start and stop a session without accidentally recording hallway conversations or the next patient.
- Correct a sentence, remove a section, and add a clinician-authored instruction before signing.
- Verify that the draft is attached to the correct patient and encounter.
- Check how the system handles a cancelled visit, a late-joining participant, a transfer between clinicians, and a co-signature.
- Simulate an outage or unsupported visit and follow the paper, dictation, or manual-entry fallback.
- Confirm that the final signed note, transcript, audio, and audit trail have the retention and access behavior you expect.
8. Assess usability, training, and support
Have representative clinicians, nurses, scribes, and administrative users perform the tasks they will actually perform. A technically accurate model can still fail if reviewing its output is slow or confusing.
- Can users see the source transcript while checking a sentence, and can they jump from a note section to the relevant audio or text?
- Are edits obvious, reversible, and attributable to the clinician rather than silently overwriting the draft?
- Can the user approve the final note only after required fields are complete?
- Are templates understandable and easy to change without vendor intervention?
- Does the interface support keyboard navigation, readable contrast, captions or text alternatives, and the devices used in examination rooms?
- What onboarding, refresher training, role-based permissions, and help-desk response times are included?
- How are clinicians informed of model updates, changed limitations, and new data-processing terms?
During the pilot, collect qualitative feedback as well as time measurements. Ask what users stopped doing because they trusted the draft, what they routinely rechecked, and which patient interactions felt less natural. Those observations often reveal risks that an accuracy percentage misses.
Rank #4

- Digital Family Calendar: BSIMB digital calendar wall touch screen puts an end to your chaotic life. Designed for busy families, the digital calendar keeps you organised and in step with your family. Assign different colours and tasks to each family member to make family scheduling easier and more intuitive.
- Easy Setup and Auto-Sync: Plug in, connect to WLAN and auto-syn your electric calendar in minutes. Digital wall calendar compatible with Google calendar, iCloud calendar, Outlook calendar, Cozi calendar and Yahoo calendar. Add events directly on the device or through the ecalendar app. Electronic calendar stays current whether you're at work or traveling—no manual updates needed.
- All-In-One Home Assistant: Smart calendar builds habits and encourage independence with personalised chores. Display daily meal plan to reduce the daily ‘What's for dinner?’ stress. To-do lists keep track of everything you want. Turning chores into valuable achievements with stars and rewards, making life easier and more enjoyable.
- Manage Anytime Anywhere: BSIMB electronic calendar for family stay connected with the powerful ecalendar app. Access and manage your digital wall calendar anytime, anywhere with free features like stars & rewards, photo screensaver, chore charts, meals plans, to-do lists etc. Electronic planner paid features like Magic Import tailor advanced tools for users with special needs.
- Stay in Touch with Loved Ones: Share photos or videos from your phone to electronic wall calendar with app, instantly update your life moment, and keep in touch with your family, especially those who are far away; you can also surprise your smart calendar digital wall by sending him a wish card; it's also great for keeping tech-illiterate elders in touch with the youngsters.
9. Evaluate total cost and contract terms
Do not compare subscription prices alone. Estimate the complete cost of implementation and ongoing operation.
What’s actually slowing this PC down?
Pick the symptom - the matching free tool is one click away.
- License or usage charges, including different rates for clinicians, locations, languages, or visit modes.
- EHR interface, API, implementation, configuration, and data-migration fees.
- Devices, microphones, network changes, support, training, and staff time for template maintenance.
- Clinician review time and any additional compliance, security, or legal work.
- Costs of storing, exporting, or deleting data at termination.
Contract review should cover permitted data uses, retention and deletion, subprocessors, breach notification, service levels, support, audit rights, liability, indemnity, ownership of generated records, export format, termination assistance, update notification, and the practice’s right to suspend or end use. Ensure the contract matches the behavior observed in the pilot; a sales demonstration is not a contractual guarantee.
10. Use a decision scorecard with pass gates
Score candidates only after defining evidence requirements. A simple scale can be useful—for example, 0 for unacceptable, 1 for major gaps, 2 for acceptable with conditions, and 3 for strong evidence—but the practice should set its own thresholds and weights.
| Criterion | Evidence to attach | Suggested pass gate |
|---|---|---|
| Clinical accuracy and completeness | Pilot error log, severity ratings, reference-note comparison | No unresolved high-severity errors; editing burden within the practice’s limit |
| Population and specialty fit | Results by language, visit type, specialty, and patient group | Acceptable performance in every approved use case, not only the average |
| Workflow and EHR integration | End-to-end task test, downtime procedure, support owner | Correct-patient association and reliable clinician approval |
| Privacy and security | Privacy policy, BAA or equivalent, security evidence, data-flow map | All mandatory controls and contractual protections verified |
| Consent and patient experience | Patient script, decline path, consent record, feedback | Clear communication and a workable alternative to recording |
| Governance and updates | Release process, incident route, audit plan, named owners | Practice can detect, investigate, and respond to changes |
| Total cost and contract | Full implementation estimate and negotiated terms | Affordable within the approved budget with acceptable exit rights |
Use hard gates for safety, privacy, correct-patient matching, and clinician approval. Do not let a high usability score compensate for a failed privacy requirement or a serious unsupported addition.
11. Roll out in controlled stages
Prepare
Finalize approved use cases, consent language, templates, access roles, fallback procedures, training, and incident definitions. Configure the product in a test environment where possible. Establish a baseline and preserve pilot records for comparison.
PC Slower Than It Used to Be?
A free scan shows the junk files, broken settings and background clutter dragging Windows down - then fixes them in one click.Free scan · Windows 10 & 11Outdated Drivers Are Slowing You Down
One free scan finds every outdated or missing driver and matches the right update for your exact hardware.Free scan · exact hardware matchLaunch narrowly
Begin with trained clinicians and a limited set of visit types. Require review before signing and make the manual workflow easy to use. Track every high-severity error, near miss, patient refusal, outage, wrong-patient event, and unexplained change in editing time.
Review before expansion
The governance group should examine accuracy by subgroup, clinician feedback, patient experience, support tickets, privacy events, and contract or model changes. Expand only when the evidence meets the pre-set gates. Keep some visit types excluded if the tool is not reliable for them.
Monitor continuously
Launch is the beginning of oversight. Audit a sample of signed notes, repeat targeted tests after material updates, review incidents and near misses, collect patient and clinician feedback, and retrain staff when workflows change. Recheck privacy materials, subprocessors, retention settings, and agreements whenever the vendor changes them. Assign a date and owner for each review rather than treating monitoring as an informal task.
Common failure modes and practical fixes
Choosing from a generic demo
Why it fails: The demo may use ideal audio, a simple visit, and a template unlike yours.
Fix: Require the same representative encounters and note standard for every candidate.
Counting only transcription accuracy
Why it fails: A correct transcript can still produce an incomplete or misleading note.
Fix: Grade the generated note for omissions, additions, attribution, negation, required fields, and editing time.
Assuming “HIPAA compliant” answers every privacy question
Why it fails: Compliance depends on your role, configuration, contract, data flows, and jurisdiction.
Fix: Review the BAA or equivalent, actual terms, retention, training use, subprocessors, access, and deletion controls.
Making recording mandatory without a decline path
Why it fails: It can conflict with local consent rules and damage patient trust.
Fix: Explain the process, document consent where required, and maintain a non-recording alternative.
Ignoring updates after procurement
Why it fails: Model, interface, and data-processing changes can alter performance or obligations.
Fix: Require update notices, repeat targeted validation, and give a named owner authority to pause use.
Measuring average savings only
Why it fails: Averages can hide poor performance for a language, accent, specialty, or high-risk visit type.
Fix: Report subgroup results and severity-weighted errors, and exclude use cases that do not meet their own gates.
Bottom line
Buy or deploy an AI medical scribe only when it has demonstrated a safe fit for your actual patients, encounters, documentation rules, EHR workflow, and legal obligations. A representative pilot, explicit data and consent controls, clear contract terms, and mandatory clinician review are more reliable decision tools than a feature list or a vendor’s overall accuracy claim. Keep governance active after launch so the practice can detect errors, respond to incidents, and reassess the system when the product or its use changes.
Quick Recap
Product prices and availability are accurate as of the date/time indicated and are subject to change. Any price and availability information displayed on Amazon at the time of purchase will apply.

