Mismatch-repair (MMR) and microsatellite-instability (MSI) tests examine a colorectal tumor for DNA-repair failure. When a tumor is mismatch-repair deficient (dMMR) or microsatellite-instability high (MSI-H), that result can make immune-checkpoint therapy an option—especially in advanced colorectal cancer—but it is not a prescription or a guarantee of response. The tests also can raise the question of inherited Lynch syndrome, which requires separate evaluation.
What the results mean
Mismatch repair and dMMR
Cells routinely copy DNA when they divide. Mismatch-repair proteins find and correct some copying errors. In a mismatch-repair-deficient (dMMR) tumor, that repair function is not working normally. The defect can involve loss or abnormal function of proteins such as MLH1, MSH2, MSH6 or PMS2.

As an Amazon Associate I earn from qualifying purchases.
MMR is a biological process; dMMR describes a deficiency in that process within the tumor. It is commonly assessed by immunohistochemistry (IHC), which looks for the presence or loss of MMR proteins in tumor cells. A pathology report may identify the specific protein or pair of proteins that is absent, which can help clinicians understand the likely repair pathway involved.
Microsatellite instability and MSI-H
Microsatellites are short, repeated DNA regions. When mismatch repair fails, the lengths of these regions can change as copying errors accumulate. A molecular MSI test examines tumor tissue for those length differences. A result reported as microsatellite-instability high (MSI-H) means the measured instability is high.
#1 Best Overall
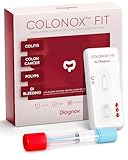
- Clinical Grade Stool Test Kit - Colonox FIT by Diagnox is an at-home stool test kit that detects hidden or occult blood in your stool, which may be a sign of GI or colorectal disorders.
- Affordable Complete Kit - Colonox FIT has everything you need. The kit includes a collection tube, antibody test, and collection apper with instructions for quick and seamless sampling & testing.
- Rapid & Easy to Read Results - Get accurate and easy-to-read results within 10 min. Look for two lines for a positive result, indicating the presence of blood, or only one line for a negative result.
- Highly Sensitive - The Colonox FIT uses antibodies to detect hemoglobin in your stool. This clinical-grade test is sensitive enough to detect hemoglobin concentrations as low as 45 ng/mL.
- Certified CLIA Waived - The Colonox FIT is a CLIA-waived test and FDA-cleared for home use. Gain reliable medical-grade insights from the comfort of your home.
dMMR and MSI-H are closely related biomarker findings, but they are not the names of one identical test. IHC asks whether particular repair proteins are missing; molecular testing asks whether the tumor DNA shows the instability pattern. Most tumors with one finding have the other, but results can be uncertain or discordant.
| Term | What it describes | Common way it is assessed |
|---|---|---|
| MMR | The DNA-copying repair process | Usually inferred from tumor protein staining |
| dMMR | Deficient mismatch-repair function in the tumor | IHC showing loss of one or more MMR proteins |
| MSI | Changes in the lengths of selected repeated DNA regions | Molecular genetic testing of tumor tissue |
| MSI-H | A high level of microsatellite instability | A molecular MSI assay on tumor DNA |
In everyday language, MSI-H is a laboratory description of the tumor’s DNA pattern, while dMMR is a description of the repair machinery. Both can be used to identify the same clinically important subgroup, but the wording on a report tells you which method produced the result. Asking for the exact test name and interpretation is more useful than treating the abbreviations as interchangeable labels.
Why oncologists order these tests
An MSI-H or dMMR result identifies a subgroup of colorectal cancers that may be more visible to the immune system and may respond to immune-checkpoint inhibitors. In practice, the result becomes one part of a treatment decision alongside the cancer’s stage, prior treatment, overall health, other tumor findings, potential risks and the patient’s preferences.
The evidence and U.S. approvals discussed here concern colorectal cancer. “Bowel cancer” is a broader reader-facing term; a result or approval for colorectal cancer should not automatically be extended to every cancer of the bowel, every stage or every country. The same biomarker may be discussed differently in other tumor types or under other regulators.
The National Cancer Institute has estimated that about 5% of people with advanced colorectal cancer have MSI-H/dMMR tumors. That is an estimate for the advanced-cancer setting described by NCI, not a universal percentage for all colorectal cancers, stages or populations.
Testing may be performed on a biopsy or a surgical specimen. The laboratory needs enough viable tumor and an interpretable sample. A report that says “indeterminate,” “insufficient,” or notes an unusual staining pattern is not the same as a confirmed negative result. The oncology and pathology teams can explain whether another block of tissue or a different method is feasible.
How testing is done on a tumor
IHC for MMR proteins
A pathology laboratory stains a tumor sample for the MMR proteins. Loss of staining for one or more proteins suggests dMMR and can indicate which repair pathway deserves closer investigation. The interpretation depends on the quality and adequacy of the specimen and on the pattern reported by the laboratory. Normal staining does not answer every hereditary-risk question, and abnormal staining does not by itself prove an inherited mutation.
Molecular MSI testing
A molecular test compares selected microsatellite regions in tumor DNA, looking for differences in their lengths. The laboratory classifies the degree of instability; MSI-H indicates a high level. This is a genetic test performed on tumor tissue, not a blood test for inherited risk. It evaluates the tumor’s acquired characteristics, even though some tumors acquire those characteristics because of an inherited repair-gene defect.
Rank #2
- Clinical Grade Stool Test Kit - Colonox FIT by Diagnox is an at-home stool test kit that detects hidden or occult blood in your stool, which may be a sign of GI or colorectal disorders.
- Affordable Complete Kit - Colonox FIT has everything you need. The kit includes a collection tube, antibody test, and collection apper with instructions for quick and seamless sampling & testing.
- Rapid & Easy to Read Results - Get accurate and easy-to-read results within 10 min. Look for two lines for a positive result, indicating the presence of blood, or only one line for a negative result.
- Highly Sensitive - The Colonox FIT uses antibodies to detect hemoglobin in your stool. This clinical-grade test is sensitive enough to detect hemoglobin concentrations as low as 45 ng/mL.
- Certified CLIA Waived - The Colonox FIT is a CLIA-waived test and FDA-cleared for home use. Gain reliable medical-grade insights from the comfort of your home.
Why clinicians may use both methods
IHC and molecular testing measure different consequences of the same repair problem. A clear result from one method can be useful, while a questionable result, a poor specimen or a mismatch between methods may require another review. NCI’s 2025 report noted that local hospital test results in a clinical-trial population were sometimes incorrect when compared with central expert confirmation. The experts cited in that report encouraged guidance calling for “two testing methodologies and referral to an expert diagnostic center in cases of uncertainty.”
That statement does not establish one universal confirmatory test or a single false-result rate. The appropriate next step depends on the actual pathology report, available tissue and the expertise of the treating and diagnostic teams. A second review may involve rereading the original slides, repeating IHC, performing molecular MSI testing, or sending material to a specialist laboratory.
Patients can ask whether the result was generated locally or centrally, whether internal controls on the stain were satisfactory, and whether the laboratory classified the result as definitive. These practical details can clarify why a treatment discussion is proceeding or why confirmation is being requested.
Do these 3 things before closing this tab:
1Fix the driver behind crashes, sound loss and screen glitches2Clear out junk files and repair common Windows errors3Scan for outdated or missing drivers - takes under a minuteWhat an MSI-H/dMMR result can change in treatment
Pembrolizumab as an initial option in advanced disease
In the United States, pembrolizumab was FDA-approved in 2020 for treatment-naive metastatic colorectal cancer that is dMMR or MSI-H. “Treatment-naive” here means the initial systemic-treatment setting for metastatic disease, not every newly diagnosed bowel cancer. The approval does not mean that every person with an MSI-H result should receive the drug; stage, fitness, contraindications and local guidance still matter.
The National Cancer Institute’s colon-cancer treatment summary reports results from the phase III KEYNOTE-177 trial. In the trial population with MSI-H/dMMR metastatic colorectal cancer, median progression-free survival was 16.5 months with pembrolizumab and 8.2 months with chemotherapy. The reported objective response rates were 43.8% and 33.3%, respectively.
These are comparisons between study groups. They are not a forecast for an individual person, and they do not show that every MSI-H/dMMR tumor will respond or that chemotherapy is never needed. A clinician may still discuss chemotherapy, surgery for selected disease, clinical trials or other approaches depending on the complete situation.
Nivolumab plus ipilimumab in the initial advanced setting
On May 2, 2025, NCI reported that the FDA had approved nivolumab plus ipilimumab for initial treatment of some people with advanced MSI-H/dMMR colorectal cancer. The report summarized the CheckMate-8HW trial: at three years, approximately 68% of people receiving the combination were alive without disease progression, compared with 51% receiving nivolumab alone.
Quick wins for a faster PC:
Clear out junk files and repair common Windows errorsFree Scan →Fix the driver behind crashes, sound loss and screen glitchesFind Drivers →Repair Windows errors before they cause bigger problemsFix Now →NCI’s account describes the combination as a preferred first-line option for some patients, while also noting concern about increased side effects with combination treatment. That is an expert view in a particular clinical context, not a rule that the combination is best for everyone. A clinician must weigh potential benefit, monitoring and toxicity against the person’s medical history and preferences. Combination therapy can require a different conversation about the intensity of monitoring and the consequences of immune-related complications.
Rank #3

- What is ColoTest? ColoTest is an at-home stool test kit that allows you to test for blood in the stool in the comfort of your own home. The test does not require a prescription and results can be read at home as soon as 1 minute of taking the test
- Why ColoTest? ColoTest detects blood in the stool, which may be an early warning for: Colorectal conditions, Diverticulitis, Gastrointestinal Disorders, Colitis & Polyps. No mail-in lab testing, no prep, and no diet restrictions required before use
- What does a positive result mean? A positive result may indicate invisible blood in the stool. This should be confirmed by your doctor with additional diagnostic procedures, likely including a colonoscopy. ColoTest is 98.8% accurate
- How often should ColoTest be used? ColoTest is recommended as an annual screening method. Bleeding in the digestive system may be intermittent. If concerned, test on three different days using new samples to increase the chances of detection
- Who is ColoTest for? Those wanting to take control of their colon health; have had a negative past experience with colonoscopy; uninsured, insurance does not cover a colonoscopy; might be expreriencing symptoms related to gastrointestinal disorders
Carmen Allegra, M.D., an NCI gastrointestinal-therapeutics adviser, said that “it’s now clear that there’s a benefit” to combining nivolumab with ipilimumab. This is an expert comment about the reported evidence, not a directive for every patient or a substitute for an individualized discussion.
| Option described in U.S. sources | Setting | Evidence figure reported by NCI | Important qualification |
|---|---|---|---|
| Pembrolizumab | Initial treatment of metastatic dMMR/MSI-H colorectal cancer | KEYNOTE-177: median progression-free survival 16.5 months versus 8.2 months with chemotherapy; objective response 43.8% versus 33.3% | Trial results for a defined population, not an individual prediction |
| Nivolumab plus ipilimumab | Initial treatment for some people with advanced dMMR/MSI-H colorectal cancer; FDA approval reported May 2, 2025 | CheckMate-8HW: approximately 68% versus 51% alive without progression at three years compared with nivolumab alone | Combination therapy may bring greater side-effect concerns; eligibility and choice are individualized |
Single-agent versus combination treatment
The main comparison is not simply which drug has the larger headline number. Clinicians also consider whether a person is suited to single-agent treatment, whether combination treatment offers a meaningful additional benefit in that setting, how much monitoring is practical, and how the person values potential benefit against toxicity. Comorbidities, concurrent medicines and previous immune problems can influence the balance. Local guidelines and regulatory wording should be checked at the time treatment is chosen.
What the result does not do
- It does not diagnose a particular stage of cancer.
- It does not guarantee that an immune-checkpoint inhibitor will work.
- It does not mean chemotherapy, surgery, radiation or other care is automatically excluded.
- It does not establish that a drug approved in the United States is approved or covered in another country.
- It does not determine the dose, schedule or monitoring plan without a clinician’s review.
How the oncology team uses the result in a real decision
- Confirm the disease setting. The treatment evidence cited above concerns advanced or metastatic colorectal cancer, especially the initial systemic-treatment setting. Earlier-stage disease and cancers outside the studied setting require different evidence and guidelines.
- Review the actual pathology report. The team checks whether the report says dMMR, pMMR, MSI-H or another category, which method was used, whether the specimen was adequate and whether the interpretation is confident.
- Check for discordance or uncertainty. If IHC and MSI do not agree, or the result is technically uncertain, the oncologist may request pathology review, another method or consultation with an expert diagnostic center.
- Discuss treatment alternatives. Options can include a single-agent checkpoint inhibitor, combination immunotherapy or non-immunotherapy treatment, depending on the disease and the person. The clinician considers comorbidities, other medicines, likely monitoring, potential toxicity and the patient’s priorities.
- Verify current local status. U.S. FDA approvals, national guidelines, insurance policies and availability can change. A team must apply the rules in the jurisdiction where treatment will be delivered.
- Plan follow-up. The team explains how response and possible toxicity will be monitored and when a new symptom should be reported. The exact schedule depends on the regimen and the patient’s condition.
The point of the biomarker is to make the discussion more informed, not to replace it with an automatic regimen. A result can open a treatment option while still leaving several reasonable choices.
The Tool Desk
Outbyte PC Repair FREEClear out junk files and repair common Windows errorsFree Scan →Outbyte Driver Updater FREEScan for outdated or missing drivers - takes under a minuteDriver Scan →What if MSI and MMR results do not match?
A mismatch can reflect technical limitations, specimen quality, an unusual tumor biology or an interpretation that needs expert review. It should not be resolved by assuming that one abbreviation is always correct. Discordance can matter because treatment eligibility and hereditary-risk discussions may depend on which result is confirmed.
Ask the oncology team:
- Which test produced each result—MMR IHC, molecular MSI testing or both?
- Was enough viable tumor present for a reliable analysis?
- Does the staining pattern point to loss of a specific MMR protein?
- Should the tissue be retested with a second methodology or reviewed by an expert diagnostic center?
- How would a confirmed result alter the treatment options for this stage of disease?
- Could the result affect recommendations for genetic counseling or testing?
NCI’s cited expert advice supports using two testing methodologies and referral when uncertainty remains. The treating team can decide whether that means repeating IHC, performing molecular MSI testing, reviewing the slides or sending material to a specialist laboratory. There is no evidence here for one mandatory sequence for every patient.
Does MSI-H mean Lynch syndrome?
No. MSI-H/dMMR is a finding in the tumor. It can be associated with Lynch syndrome, an inherited cancer-predisposition condition, but the tumor result alone does not prove that the mutation was inherited.
Lynch-associated tumors may involve inherited defects in MLH1, MSH2, MSH6 or PMS2. A different mechanism—silencing of a repair gene through DNA methylation—can also produce an MSI-H tumor without Lynch syndrome. MSI-H is therefore seen both in Lynch-associated tumors and in a smaller portion of colon cancers that are not associated with Lynch syndrome.
Free tools Windows power users keep installed
One-click scans. No signup required.
What hereditary-risk evaluation may involve
If the tumor pattern raises concern, clinicians may discuss genetic counseling and germline testing. Germline testing examines inherited DNA, usually from a blood or saliva sample, and answers a different question from tumor MSI or IHC. Family history, age at diagnosis, the specific protein-loss pattern and other clinical details can influence whether counseling or testing is recommended.
A hereditary result can affect relatives and future cancer screening, so it should be interpreted with qualified genetic professionals. It should not be inferred from MSI-H alone. A negative germline result may also need context, because the tumor can have a non-inherited cause.
Independent reader supportYour contribution helps us test, update, and keep practical guides available for everyone.Questions to bring to an appointment
- Is my cancer colorectal, and what stage and treatment setting are we discussing?
- Does my report show dMMR, MSI-H, both, or an indeterminate result?
- Which laboratory method was used, and was the tissue adequate?
- If the results disagree, should another method or expert review be obtained?
- Do the findings make an immune-checkpoint inhibitor an option for my situation under current local guidance?
- Would single-agent or combination treatment be considered, and why?
- What monitoring is needed, and what potential side effects should prompt a call?
- What are the alternatives if immunotherapy is unsuitable or ineffective?
- Does my tumor result warrant genetic counseling or germline testing for possible Lynch syndrome?
How to interpret the headline numbers
The KEYNOTE-177 and CheckMate-8HW figures describe groups of people selected for particular clinical and biomarker criteria. Median progression-free survival is the time by which half the trial population had experienced progression or another defined event; it is not a promised duration for an individual. An objective response rate is the proportion whose tumors met the study’s response criteria, not the chance that every patient will benefit in the same way.
The three-year “alive without progression” figure in CheckMate-8HW is also a group-level outcome. It does not mean that a particular person has a 68% or 51% personal probability, because eligibility, follow-up, disease characteristics and treatment tolerance differ. Trial comparisons are useful for understanding relative evidence, but they cannot replace an individualized estimate.
Outdated Drivers Are Slowing You Down
One free scan finds every outdated or missing driver and matches the right update for your exact hardware.Free scan · exact hardware matchPC Slower Than It Used to Be?
A free scan shows the junk files, broken settings and background clutter dragging Windows down - then fixes them in one click.Free scan · Windows 10 & 11Age, tumor burden, other illnesses, previous treatment, immune-related risks, access to specialist care and many unmeasured factors can change an individual experience. The safest use of these statistics is to understand why the biomarker matters and to frame a discussion with the oncology team.
Practical limits and changing guidance
The approvals and figures described here are U.S.-focused. Regulatory decisions, reimbursement and clinical guidelines can change, and a medicine may be available in one country but not another. Even within the United States, an insurer may require documentation of biomarker status or a particular treatment setting. The oncology team or cancer center can verify the current rules rather than relying on an old report or a general internet summary.
Testing is also not infallible. Tissue can be limited, stains can be difficult to interpret and molecular results can be technically unresolved. That is why a careful report, review of discordant findings and expert consultation matter. A test result should be read together with the pathology narrative and the clinical history, not as an isolated line in the chart.
Frequently Asked Questions
What does MSI-high mean?
MSI-high means a tumor’s DNA has a high level of length changes in selected microsatellite regions. It is a molecular finding associated with mismatch-repair failure and can identify advanced colorectal cancers for which checkpoint immunotherapy may be considered.
What’s actually slowing this PC down?
Pick the symptom - the matching free tool is one click away.
What is the difference between dMMR and MSI-H?
dMMR describes deficient mismatch-repair function, often identified by loss of MMR proteins on IHC. MSI-H describes a high-instability DNA pattern measured by molecular testing. They are related findings from different methods, not one identical test.
Best Value

- Test Early, Monitor Timely : INDICAID iFOB Test monitors hidden or occult blood in stool. Test for Ulcers, Polyps, Colitis
- High Sensitivity and Accuracy : FDA 510(k) Cleared iFOB home test kit is sensitive enough to monitor low levels of hemoglobin in stool
- Cost-Effective : FSA/HSA reimbursement eligibility helps make colorectal health monitoring more accessible
- Simple Process & Rapid Results : No prep needed. Simply test at home and get results in minutes
- Comprehensive at-Home Kit : Includes test cassette, collection tools, and step-by-step guide. The INDICAID iFOB test provides a reliable method for at-home stool analysis
Does MSI-H mean I have Lynch syndrome?
No. MSI-H can result from an inherited repair-gene defect, but it can also arise through non-inherited mechanisms such as DNA methylation. Genetic counseling and germline testing are separate from tumor MSI or IHC.
What happens if my MSI and MMR results do not match?
Ask whether the tissue and test controls were adequate and whether the tumor should be reviewed or tested with a second method. NCI-cited experts recommend two testing methodologies and referral to an expert diagnostic center when uncertainty remains.
Can an MSI-H result guarantee that immunotherapy will work?
No. MSI-H/dMMR status identifies a group more likely to benefit, but response is not guaranteed. Stage, overall health, other tumor features and treatment tolerance still affect the decision and outcome.
Which colorectal cancers were covered by the U.S. treatment evidence?
The cited evidence concerns advanced or metastatic MSI-H/dMMR colorectal cancer, particularly initial systemic treatment. It should not automatically be applied to every bowel cancer, earlier-stage disease or another country’s approval rules.
What immunotherapy options are described in current U.S. sources?
Pembrolizumab is an initial option for treatment-naive metastatic dMMR/MSI-H colorectal cancer. NCI reported FDA approval on May 2, 2025, for nivolumab plus ipilimumab as initial treatment for some people with advanced MSI-H/dMMR colorectal cancer. Choice is individualized, and combination therapy may bring greater side-effect concerns.
Should my family be tested if my tumor is MSI-H?
Possibly, but the tumor result alone does not establish inherited Lynch syndrome. Discuss the result, family history and protein-loss pattern with a genetic counselor or oncology team before deciding on germline testing or family evaluation.
The Bottom Line
MMR IHC and molecular MSI testing look at different aspects of the same DNA-repair problem. A confirmed dMMR or MSI-H result can make checkpoint immunotherapy an option in advanced colorectal cancer, including U.S. options such as pembrolizumab and, for some patients, nivolumab plus ipilimumab. The result is not a guarantee, does not replace staging and clinical judgment, and does not prove Lynch syndrome. When tests disagree, ask about repeat testing, expert pathology review and genetic counseling.
Recommended Free Tools
Quick Recap
Product prices and availability are accurate as of the date/time indicated and are subject to change. Any price and availability information displayed on Amazon at the time of purchase will apply.

