Average-risk screening follows a population schedule; higher-risk screening is tailored. A personal or family cancer history, an inherited gene variant, substantial carcinogen exposure, prior therapeutic radiation, or a medical condition can mean starting earlier, testing more often, choosing a different test, or continuing surveillance after routine screening would end. The right plan depends on the cancer, the specific risk factor, your age, previous results and procedures, and the current guidance from the organization that covers your situation.
What “average risk” and “higher risk” mean
“Average risk” does not mean no risk. It describes the people for whom a guideline’s standard schedule was developed, generally without a personal cancer history, a strong related family history, a known inherited susceptibility, or another factor that substantially changes the expected probability of disease. Population recommendations are designed to produce more benefit than harm across that broad group.

As an Amazon Associate I earn from qualifying purchases.
“Higher risk” is not one diagnosis or one universal schedule. It is a reason to replace the default pathway with an individualized plan. The change may involve an earlier starting age, a shorter interval between tests, a different screening method, or surveillance that continues after average-risk screening would stop. The appropriate change depends on the exact condition and on guidance for that condition; there is no single “high-risk interval” that applies to every cancer.
- Personal history: A previous cancer, ductal carcinoma in situ (DCIS), or high-risk precancerous lesion can require surveillance rather than routine population screening.
- Family history: A first-degree relative’s cancer, several affected relatives, young ages at diagnosis, or a pattern of related cancers can indicate increased risk. The strength of the signal depends on which relatives were affected and the cancer type.
- Inherited variants or syndromes: Harmful variants and syndromes such as Lynch syndrome or familial adenomatous polyposis can alter both the starting age and the tests used.
- Exposure or treatment: Substantial tobacco exposure and childhood chest radiation are examples of factors that can move someone out of an average-risk pathway.
- Medical conditions: Inflammatory bowel disease, among other conditions, is associated with higher colorectal cancer risk and can require frequent colonoscopic surveillance.
A risk factor raises probability; it does not guarantee that cancer will develop. Estimates are uncertain, and two people with the same label may still need different plans. A clinician should verify the risk category rather than assuming that “more screening” is automatically safer.
#1 Best Overall

- [Ultra-Lightweight Ear Buds Designed for Small Ears] Each earbud weighs only 3.7g and features a compact, ergonomic in-ear design made especially for small ears. Secure, low-profile, and comfortable for workouts, all-day wear or overnight sleeping.The ultra-slim profile sits flush in your ear with no hard edges poking or rubbing, so you can even sleep on your side without discomfort.
- [Immersive Stereo Sound with TOZO OrigX Technology] TOZO OrigX tuning delivers clear vocals, balanced mids, and natural stereo sound for music, podcasts, and videos.
- [Long Battery Life for Daily Use] Get up to 7 hours of playtime on a single charge, with up to 32 hours total using the charging case—ideal for workdays, commuting, and extended listening sessions.
- [Bluetooth 5.3 & Stable Connection] Bluetooth 5.3 provides fast pairing, stable wireless performance, and reduced dropouts as you move around home or office.
- [Deep Bass with Clear Vocals] High-performance drivers produce punchy bass while keeping vocals clean and detailed for everyday listening.
Why the schedule changes for higher-risk patients
Screening is intended for people who do not have symptoms. It identifies people who may need diagnostic evaluation; it does not establish a diagnosis. An abnormal mammogram, stool test, HPV result, CT scan, or PSA level therefore leads to a follow-up pathway rather than a conclusion that cancer is present.
Higher-risk plans try to account for a greater chance that disease will appear earlier or that a routine test will miss a developing lesion. Depending on the evidence for the risk factor, a guideline may recommend:
- starting before the average-risk age;
- repeating a test at shorter intervals;
- using a different test or combining methods;
- performing surveillance after treatment or removal of a precancerous lesion; or
- referring the patient for genetic counseling or specialist management.
These changes also create possible harms. False-positive results can lead to repeat imaging, biopsies, colonoscopy, or other procedures. Screening can find a disease that would never have caused symptoms or shortened life, a problem known as overdiagnosis. Anxiety, complications from follow-up, and the burden of repeated testing must be weighed against the chance of finding a clinically important cancer earlier.
At-a-glance comparison
| Decision point | Average-risk approach | Higher-risk approach |
|---|---|---|
| Eligibility | Meets the population definition used by the issuing guideline. | Has a personal or family history, inherited susceptibility, exposure, prior treatment, or condition that changes risk. |
| Starting age | Uses the guideline’s standard age range. | May begin earlier; the age is condition-specific. |
| Test | Uses the population-recommended test, such as mammography, HPV testing, stool testing, or another listed option. | May use a different test, a combination, or specialist-directed surveillance. |
| Interval | Follows the standard interval when prior results are normal. | May be shorter or vary with findings, treatment history, and the specific syndrome or condition. |
| Follow-up | An abnormal screen leads to diagnostic evaluation under the routine pathway. | Follow-up may be more intensive and may involve specialists or genetic counseling. |
| What must be considered | Age, health, expected benefit, harms, and preferences. | All average-risk factors plus the exact risk estimate, prior tests and procedures, and the applicable high-risk guidance. |
Breast cancer: a clear example of two pathways
Average-risk mammography
The National Cancer Institute (NCI) summarizes the U.S. Preventive Services Task Force recommendation for average-risk women as a mammogram every two years from ages 40 through 74. This is a population recommendation, not a rule for someone whose history places her in a different risk group. The NCI page carrying this summary was updated in 2025.
Rank #2

- 【IP68 Waterproof Multifunctinal Smart Watch】Torjalph fitness activity tracker smart watch is IP68 waterproof technology ,you can wear it when swimming,handwashing,it's rain-proof which means that you perform multiple exercise modes outside without worrying about sweat or rain corroding your fitness smart watch,and this watch equipped with a 230 mAh large capacity battery magnetic charging ,and this sports activity tracker watch can be used 5-7 days If fully charged.
- 【Larger 1.83'' Full Screen Watch & Multi-dial Selection】1.83 inch full HD color touch screen smart watch for men / women provides excellent 240*284 resolution image quality ,This Bluetooth smart watch offers a better touch experience and remarkable immersion and ,more than 200 watch faces for you to choose from App"Da Fit ", you can change the dial style according to your mood to wear keeping the world on your wrist
- 【Accurate Activity Tracker Smart Watch 】sports watch activity tracker uses sweat and dust resistant breathable silicone strap, our Fitness Tracker Smart Watch for Android iOS Phones supports 12 sports modes,walking,running,bicycle,swimming,badminton,basketball,football,rope skipping. This bluetooth calls smart watch for men women is lightweight and stylish, bringing more convenient and relaxing sports experience while also providing more protection.
- 【Your 24 Hour Personal Daily Health Monitor】Fitness watch for women men full touch screen IP67 waterproof bluetooth smartwatch for Android iOS Phones with heart rate blood pressure monitor multifunction Andriod smart watch with steps counter sleep monitor sports fitness watch, monitoring blood oxygen saturation allows you to understand your physical condition in real time to track fitness progress ,to know your health status in time.
- 【More Functions Bluetooth Call Smart Watch】This fitness activity smart watch full screen for iPhone and Android phones includes a bunch of new features including:The bluetooth smart watch can hang up the phone, receive and display WhatsAPP /Text /Facebook /Twitter /Messenger reminder.Support sedentary reminder, alarm clock, stopwatch, timer,weather information,music control, remote camera control compatible with Android 5.0 and above or iOS 9.0 and above smartphones.
When earlier or more frequent screening is discussed
NCI identifies known harmful BRCA1 or BRCA2 variants and chest or breast radiation received during childhood cancer treatment as examples of very high risk. People in these groups may be advised to begin screening younger, screen more frequently, or use a different combination of tests. The exact plan should come from the relevant specialty or high-risk clinic rather than from the average-risk mammography interval.
Other factors associated with increased breast cancer risk include a family history, inherited gene changes, a previous breast cancer or DCIS, and breast density. These factors do not all carry the same level of risk, and individual estimates remain uncertain. A clinician may need the ages and diagnoses of relatives, pathology from prior lesions, treatment records, and any genetic test report before choosing an interval.
What happens after an abnormal result
A screening mammogram is not a diagnosis. The next step can include additional mammographic views, ultrasound, magnetic-resonance imaging, or a biopsy, depending on the finding and the person’s risk. Higher-risk surveillance does not eliminate false positives; it is a deliberate trade-off that accepts more follow-up in exchange for a chance of earlier detection.
The Tool Desk
Outbyte Driver Updater FREEFix the driver behind crashes, sound loss and screen glitchesFind Drivers →Outbyte PC Repair FREEClear out junk files and repair common Windows errorsFree Scan →Colorectal cancer: history determines the pathway
Average-risk starting point
NCI states that average-risk colorectal screening generally begins at age 45. Current guidance offers stool-based tests and visualization procedures; the choice should fit the person’s health, ability to complete preparation, access to follow-up, and preferences. A positive stool test is not a diagnosis and normally requires a diagnostic colonoscopy.
Rank #3
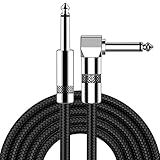
- [Low Noise High Fidelity] New bee guitar cord with 22AWG oxygen-free-copper center conductors provides enhanced signal transfer, the PVC insulation material and the high-density stranded copper double shield provide noise rejection for quiet operation
- [Ideal for Choice] New bee 1/4 straight and right angle metal connectors, ensures a secure connection in any instrument, pedal, or amp jack. L shape great fro on stage guitar stands
- [Wide Compatible] Suitable for mixer, power amplifier, microphone, effector, decoder, equalizer, electoronic organ, electric guitar, electric bass and other electronic equipments. Widely used in the installation of smart home, karaoke speaker, professional stage audio, etc
- [Easy Disassemble] Making incidental repairs quick and easy! Very nice, flexible cable
- [Dont Hesite to Order] 24 hours customer services and professional technology team are standing by
Factors that change screening
A first-degree family history, an inherited syndrome such as Lynch syndrome or familial adenomatous polyposis, a personal history of colorectal cancer or high-risk adenomas, and inflammatory bowel disease can all move a patient out of the average-risk pathway. Inflammatory bowel disease is associated with increased colorectal cancer risk, and the NCI professional summary notes that frequent colonoscopic surveillance is recommended; the interval must be taken from condition-specific guidance.
Because these conditions differ greatly, it would be unsafe to apply one universal interval. The plan may depend on the relative’s age at diagnosis, the number and type of adenomas, the extent and duration of inflammatory bowel disease, genetic test results, and findings on earlier colonoscopies. Bring prior procedure reports and pathology, not just the memory that a test was “normal” or “abnormal.”
Choosing among tests
Stool tests are completed at home but must be repeated on their specified schedule and followed by colonoscopy when positive. Visualization procedures can detect and sometimes remove lesions during the examination, but they require preparation and carry procedural burdens. For higher-risk patients, a clinician may determine that a visualization strategy is more appropriate than a population stool-testing option. The decision should be consistent with current guidance for the specific risk factor.
Free tools Windows power users keep installed
One-click scans. No signup required.
Cervical cancer: age and health history both matter
Average-risk screening
HPV tests and Pap tests are screening methods, and the appropriate test and timing depend on age and health history. NCI reports the American Cancer Society recommendation to begin primary HPV testing at age 25 and repeat it every five years through age 65 for people who meet the average-risk criteria and have adequate prior screening.
Rank #4

- Digital Family Calendar: BSIMB digital calendar wall touch screen puts an end to your chaotic life. Designed for busy families, the digital calendar keeps you organised and in step with your family. Assign different colours and tasks to each family member to make family scheduling easier and more intuitive.
- Easy Setup and Auto-Sync: Plug in, connect to WLAN and auto-syn your electric calendar in minutes. Digital wall calendar compatible with Google calendar, iCloud calendar, Outlook calendar, Cozi calendar and Yahoo calendar. Add events directly on the device or through the ecalendar app. Electronic calendar stays current whether you're at work or traveling—no manual updates needed.
- All-In-One Home Assistant: Smart calendar builds habits and encourage independence with personalised chores. Display daily meal plan to reduce the daily ‘What's for dinner?’ stress. To-do lists keep track of everything you want. Turning chores into valuable achievements with stars and rewards, making life easier and more enjoyable.
- Manage Anytime Anywhere: BSIMB electronic calendar for family stay connected with the powerful ecalendar app. Access and manage your digital wall calendar anytime, anywhere with free features like stars & rewards, photo screensaver, chore charts, meals plans, to-do lists etc. Electronic planner paid features like Magic Import tailor advanced tools for users with special needs.
- Stay in Touch with Loved Ones: Share photos or videos from your phone to electronic wall calendar with app, instantly update your life moment, and keep in touch with your family, especially those who are far away; you can also surprise your smart calendar digital wall by sending him a wish card; it's also great for keeping tech-illiterate elders in touch with the youngsters.
Why the average schedule may not apply
A history of cervical precancer or cancer, immune suppression, treatment that affects the cervix, or inadequate prior screening can require a different follow-up plan. The exception must be verified against the relevant guideline because the correct interval depends on the diagnosis and previous results. A positive HPV or abnormal Pap result calls for risk-based follow-up, not an assumption that cancer is present.
Screening can stop at a guideline’s upper age only when the person meets that guideline’s health-history and prior-screening requirements. Someone with a high-risk history may need continued surveillance even when an average-risk schedule would end.
Independent reader supportYour contribution helps us test, update, and keep practical guides available for everyone.Lung cancer: screening is for a selected smoking-exposure group
Low-dose computed tomography (LDCT) is not a general population scan. NCI describes it as a screening test for people with a substantial smoking history. Eligibility is based on smoking exposure and other factors specified by current guidance, so a person should not order a CT simply because a relative had lung cancer or because of a nonspecific concern.
Do these 3 things before closing this tab:
1Clear out junk files and repair common Windows errors2Scan for outdated or missing drivers - takes under a minute3Repair Windows errors before they cause bigger problemsLDCT can produce findings that require repeat imaging or invasive evaluation. The potential benefit of finding a treatable lung cancer earlier has to be balanced against false positives, incidental findings, and downstream procedures. A clinician can confirm whether the person meets the current eligibility criteria and explain how abnormal findings are managed.
Prostate cancer: PSA is a preference-sensitive decision
PSA testing is not a simple, universal instruction for every man. NCI describes it as a decision that weighs potential benefits and harms in light of personal risk and preferences. Age, family history, inherited susceptibility, race and ethnicity, prior results, and overall health can affect the discussion, but the test does not by itself distinguish an aggressive cancer from a harmless condition.
A higher PSA can lead to repeat testing, imaging, or biopsy; a lower value does not guarantee that cancer is absent. Before testing, ask what result would lead to another procedure, what the possible outcomes are, and whether finding a slow-growing cancer would change treatment. Shared decision-making is part of the screening process, not an optional conversation after the blood draw.
How to work out your own screening plan
- Write down the relevant history. Include your cancers or precancerous findings, biopsies, adenomas, prior radiation or other cancer treatment, inflammatory bowel disease, immune-related conditions, tobacco exposure, and every screening result you can document.
- Map your family history. Record the cancer type, whether the relative is a first-degree relative, and the age at diagnosis. Several relatives with related cancers or unusually young diagnoses deserve particular attention.
- Collect genetic information. Bring the laboratory report for any inherited-variant test. A relative’s reported mutation should be confirmed rather than copied from memory or an online family tree.
- Identify the issuing guidance. Recommendations differ among organizations and change over time. Ask which organization’s guideline applies to your cancer and risk factor and what date or version the clinician is using.
- Choose the test and interval together. Discuss the expected benefit, the chance of a false positive or overdiagnosis, preparation and procedure burdens, and how a positive result will be evaluated.
- Set the follow-up before testing. Know who will receive the result, how quickly it will be reviewed, and what diagnostic test follows an abnormal screen. A screening program is incomplete if positive results cannot be evaluated.
- Reassess after new information. A new diagnosis in the family, a genetic result, a polyp, an abnormal screen, or a change in treatment history can move you to a different pathway.
Common mistakes and safer alternatives
- Using a relative’s schedule: Two relatives can have different cancers, ages, and genetic findings. Ask for an assessment based on your documented history.
- Assuming earlier is always better: Earlier testing can increase false positives and procedures. Confirm that the expected benefit outweighs those harms for your risk group.
- Treating a screening result as a diagnosis: Screening flags people for evaluation. Only diagnostic follow-up can determine what an abnormal result means.
- Applying an average-risk interval after treatment: Prior cancer, DCIS, high-risk adenomas, or childhood chest radiation may require surveillance that does not match the population schedule.
- Ignoring a positive test because you feel well: Screening is performed in people without symptoms; feeling healthy does not replace the recommended follow-up.
- Relying on an undated recommendation: Screening guidance changes. Confirm the current recommendation and the organization that issued it.
When to ask for specialist help
Request a genetics professional, high-risk clinic, gastroenterologist, breast specialist, or other relevant specialist when a family pattern is strong, a harmful inherited variant is known or suspected, a prior treatment may alter risk, or a condition such as inflammatory bowel disease requires surveillance. Bring original pathology, imaging, operative notes, radiation summaries, and genetic reports when available. Specialist input is especially useful when guidelines leave more than one reasonable option and the choice depends on your values.
Recommended Free Tools
What the evidence can—and cannot—tell you
NCI’s summaries provide U.S.-oriented examples, including average-risk mammography every two years from 40 through 74, colorectal screening generally beginning at 45, and the ACS average-risk cervical schedule beginning with HPV testing at 25. They are educational summaries, not a substitute for an individual medical-care decision. Organizations may differ, and recommendations can change. A schedule that is correct for one cancer or one inherited syndrome may be wrong for another.
The practical distinction is therefore not “screen often” versus “screen rarely.” It is whether the plan matches the person’s actual risk, uses the appropriate test, includes a clear response to abnormal findings, and acknowledges both early-detection benefits and screening harms.
Quick Recap
Product prices and availability are accurate as of the date/time indicated and are subject to change. Any price and availability information displayed on Amazon at the time of purchase will apply.

