Neither treatment is universally “better.” CAR T-cell therapy and bispecific antibodies both direct a patient’s T cells against cancer, but they differ in how the immune cells are prepared, how quickly treatment can begin, how often treatment is given, and which risks are most prominent. The right comparison depends on the cancer type, treatment line, target, prior therapies, overall health, urgency of disease control, and the evidence available for that exact situation.
This guide explains the biology, treatment journeys, safety issues, evidence limits, and practical questions to take to an oncology team. It is general information, not a recommendation for an individual treatment plan.

As an Amazon Associate I earn from qualifying purchases.
The short answer: the disease setting determines the comparison
CAR T-cell therapy is a one-time infusion of a patient’s own T cells after they are collected, genetically modified in a laboratory to recognize a cancer target, multiplied, and returned to the body. The National Cancer Institute (NCI) describes the process from collection to infusion as taking about three to five weeks, although the exact schedule depends on the product, manufacturing process, clinical condition, and treatment center (NCI overview of T-cell transfer therapy; NCI explanation of CAR T cells).
A bispecific antibody is an engineered antibody that binds a target on a cancer cell and CD3 on a T cell. It brings the patient’s existing T cells into contact with the cancer inside the body. In the relapsed or refractory B-cell lymphoma setting discussed by the American Society of Hematology (ASH), these medicines avoid individualized cell manufacturing but usually require repeated injections or infusions (ASH, “CARs vs bispecifics: the race is on!”).
#1 Best Overall

- [Ultra-Lightweight Ear Buds Designed for Small Ears] Each earbud weighs only 3.7g and features a compact, ergonomic in-ear design made especially for small ears. Secure, low-profile, and comfortable for workouts, all-day wear or overnight sleeping.The ultra-slim profile sits flush in your ear with no hard edges poking or rubbing, so you can even sleep on your side without discomfort.
- [Immersive Stereo Sound with TOZO OrigX Technology] TOZO OrigX tuning delivers clear vocals, balanced mids, and natural stereo sound for music, podcasts, and videos.
- [Long Battery Life for Daily Use] Get up to 7 hours of playtime on a single charge, with up to 32 hours total using the charging case—ideal for workdays, commuting, and extended listening sessions.
- [Bluetooth 5.3 & Stable Connection] Bluetooth 5.3 provides fast pairing, stable wireless performance, and reduced dropouts as you move around home or office.
- [Deep Bass with Clear Vocals] High-performance drivers produce punchy bass while keeping vocals clean and detailed for everyday listening.
Both approaches can produce cytokine release syndrome (CRS), an inflammatory reaction caused by immune activation. CAR T therapy has a recognized risk of immune effector cell-associated neurotoxicity syndrome (ICANS), while bispecific-antibody toxicity varies by product, cancer subtype, route, and dosing schedule. In a 2024 ASH summary of a meta-analysis involving third-line-or-later large B-cell lymphoma, CAR T studies had higher pooled complete-remission and progression-free-survival rates than bispecific-antibody studies, but also more adverse events. Those data came from pooled, non-randomized evidence rather than a randomized head-to-head trial, so they do not establish a universal ranking.
How CAR T-cell therapy works
Collection and laboratory engineering
CAR T begins with leukapheresis, a procedure that separates T cells from the blood and returns the remaining blood components. The collected cells are sent to a specialized laboratory. There, a gene is introduced so the T cells make a chimeric antigen receptor (CAR) designed to recognize a specific cancer-associated target. The modified cells are expanded until there are enough for treatment and then undergo quality testing.
The NCI describes CAR T-cell therapy as changing a patient’s T cells in the laboratory so they bind to cancer cells and kill them (NCI, T-cell Transfer Therapy). Because the cells are made for that patient, manufacturing capacity, test results, and the patient’s clinical condition all affect the path to infusion.
The Tool Desk
Outbyte Driver Updater FREEScan for outdated or missing drivers - takes under a minuteDriver Scan →Outbyte PC Repair FREERepair Windows errors before they cause bigger problemsFix Now →Preparation before infusion
Patients may receive “bridging” treatment while their cells are being manufactured if the cancer needs control during the waiting period. Shortly before the infusion, a lymphodepleting chemotherapy regimen is commonly used to make room for the infused cells and support their expansion. The exact drugs, timing, and eligibility requirements are product- and protocol-specific.
Infusion and monitoring
The engineered cells are infused after the treatment center confirms that the product passed release testing and that the patient remains eligible. The infused CAR T cells can multiply and remain active for an extended period. Close monitoring is required after treatment because CRS, neurologic toxicity, infections, low blood counts, and other complications can occur during the early recovery period or later.
How bispecific antibodies work
One molecule connects two cells
A bispecific antibody has two binding arms with different jobs: one recognizes a protein on the cancer cell and the other recognizes CD3 on a T cell. By physically bringing the cells together, it activates the patient’s own T cells against the target cell. The T cells are not removed or genetically modified outside the body.
Rank #2

- 【IP68 Waterproof Multifunctinal Smart Watch】Torjalph fitness activity tracker smart watch is IP68 waterproof technology ,you can wear it when swimming,handwashing,it's rain-proof which means that you perform multiple exercise modes outside without worrying about sweat or rain corroding your fitness smart watch,and this watch equipped with a 230 mAh large capacity battery magnetic charging ,and this sports activity tracker watch can be used 5-7 days If fully charged.
- 【Larger 1.83'' Full Screen Watch & Multi-dial Selection】1.83 inch full HD color touch screen smart watch for men / women provides excellent 240*284 resolution image quality ,This Bluetooth smart watch offers a better touch experience and remarkable immersion and ,more than 200 watch faces for you to choose from App"Da Fit ", you can change the dial style according to your mood to wear keeping the world on your wrist
- 【Accurate Activity Tracker Smart Watch 】sports watch activity tracker uses sweat and dust resistant breathable silicone strap, our Fitness Tracker Smart Watch for Android iOS Phones supports 12 sports modes,walking,running,bicycle,swimming,badminton,basketball,football,rope skipping. This bluetooth calls smart watch for men women is lightweight and stylish, bringing more convenient and relaxing sports experience while also providing more protection.
- 【Your 24 Hour Personal Daily Health Monitor】Fitness watch for women men full touch screen IP67 waterproof bluetooth smartwatch for Android iOS Phones with heart rate blood pressure monitor multifunction Andriod smart watch with steps counter sleep monitor sports fitness watch, monitoring blood oxygen saturation allows you to understand your physical condition in real time to track fitness progress ,to know your health status in time.
- 【More Functions Bluetooth Call Smart Watch】This fitness activity smart watch full screen for iPhone and Android phones includes a bunch of new features including:The bluetooth smart watch can hang up the phone, receive and display WhatsAPP /Text /Facebook /Twitter /Messenger reminder.Support sedentary reminder, alarm clock, stopwatch, timer,weather information,music control, remote camera control compatible with Android 5.0 and above or iOS 9.0 and above smartphones.
Repeated, product-specific dosing
In the B-cell lymphoma setting described by ASH, bispecific antibodies are available without individualized cell manufacturing. Treatment is delivered in repeated doses, with the route and schedule varying by product. Early doses may be stepped up or given with additional observation to reduce and manage CRS risk. Some products are administered intravenously and others subcutaneously; the treating center follows the applicable label and protocol (ASH consensus recommendations on CD3×CD20 bispecific-antibody toxicity).
Recommended Free Tools
Because dosing continues over time, the treatment plan can involve repeated visits, laboratory checks, and decisions about holding or adjusting doses when side effects or infections occur. “Off the shelf” describes the absence of patient-specific cell manufacturing; it does not mean that every patient can start immediately or that monitoring is unnecessary.
CAR T and bispecific antibodies at a glance
| Dimension | CAR T-cell therapy | Bispecific antibodies |
|---|---|---|
| Immune mechanism | The patient’s T cells are modified outside the body to recognize a cancer target, expanded, and infused. | An antibody binds a cancer target and CD3, recruiting the patient’s existing T cells inside the body. |
| Preparation | Individualized collection, manufacturing, testing, and release. | No individualized cell manufacture in the cited lymphoma use; the antibody is manufactured in advance. |
| Timing | NCI describes about three to five weeks from collection to infusion; the actual timeline can differ. | Can avoid the manufacturing wait, but starting treatment still depends on eligibility, product availability, scheduling, and disease urgency. |
| Treatment pattern | A planned cell infusion followed by intensive monitoring and longer-term follow-up. | Repeated injections or infusions according to the product’s schedule. |
| Important toxicities | CRS, ICANS and other neurologic effects, infections, low blood counts, and other serious effects. | CRS and infections are important; neurotoxicity is generally less common and lower grade than CAR T-associated ICANS in ASH consensus guidance, but risk varies by product and setting. |
| Evidence comparison | In third-line-or-later large B-cell lymphoma, pooled studies summarized by ASH reported higher complete-remission and progression-free-survival rates than bispecific-antibody studies, with more adverse events. | The same pooled comparison does not establish superiority because it was not a randomized head-to-head trial. |
What the CAR T treatment journey involves
- Confirm the indication. The team verifies the diagnosis, cancer target, prior treatments, disease status, organ function, infection history, and other label requirements. NCI reports six approved CAR T therapies for blood cancers, but approval does not mean that every product applies to every blood cancer or treatment line (NCI treatment information).
- Complete a pre-treatment evaluation. Tests may include blood counts, chemistry studies, imaging, infection screening, heart or lung assessment, and a review of medicines. The center also evaluates whether the patient can safely undergo leukapheresis and later lymphodepleting chemotherapy.
- Collect T cells by leukapheresis. The patient is connected to an apheresis machine that separates white blood cells. The procedure may take several hours, and venous access requirements vary.
- Manufacture and test the cells. The cells are modified, expanded, and tested. NCI’s general estimate is about three to five weeks from collection to infusion, but manufacturing or clinical issues can change the timeline (NCI CAR T-cell overview).
- Manage the disease while waiting when necessary. Some patients receive bridging therapy. Whether it is appropriate depends on the cancer’s behavior, prior treatment, blood counts, infection risk, and the planned CAR T product.
- Receive lymphodepleting chemotherapy. This short course is given before the CAR T infusion according to the product and center protocol. It can temporarily worsen low blood counts and infection risk.
- Receive the CAR T infusion. The engineered cells are infused after final checks. The infusion itself may be relatively brief compared with the surrounding preparation and observation.
- Remain under close observation. The center monitors temperature, blood pressure, oxygen level, neurologic status, blood counts, and laboratory markers. Some people need hospitalization; others may be managed through a structured outpatient program with rapid access to emergency care, depending on the product and center.
- Continue long-term follow-up. Follow-up includes cancer response assessments, blood-count and immune-system monitoring, infection prevention, and surveillance for late complications. FDA labeling now includes a boxed warning about T-cell malignancies after currently approved BCMA-directed or CD19-directed genetically modified autologous CAR T products and recommends lifelong monitoring for secondary malignancies (FDA safety communication, April 18, 2024).
What a bispecific-antibody treatment journey involves
Assessment and first dose
The team first confirms that the patient’s cancer expresses the required target and that the medicine is approved or otherwise appropriate for that diagnosis and treatment line. Baseline blood tests, infection assessment, and review of neurologic and organ function help determine the safest starting plan.
Step-up dosing and observation
Many bispecific programs use a step-up schedule: initial doses are smaller or spaced in a way intended to reduce the intensity of immune activation before the treatment reaches its target dose. Observation requirements depend on the medicine, route, dose, disease, and local protocol. A fever or other symptom after an early dose may require urgent evaluation rather than simply waiting for the next appointment.
Ongoing cycles
After the initial doses, treatment continues at repeated intervals. The schedule can be weekly, every few weeks, or otherwise product-specific. Some doses may be given in an infusion center and others by injection. Laboratory monitoring and infection precautions continue throughout treatment, and clinicians may delay a dose when blood counts, infections, or other toxicities make treatment unsafe.
What’s actually slowing this PC down?
Pick the symptom - the matching free tool is one click away.
Safety: shared risks and different patterns
Cytokine release syndrome (CRS)
CRS is an inflammatory response that can occur when activated immune cells release cytokines, chemical messengers that affect the whole body. Possible symptoms listed by NCI include fever, nausea, headache, rash, rapid heartbeat, low blood pressure, and breathing difficulty (NCI T-cell transfer therapy information).
Rank #3
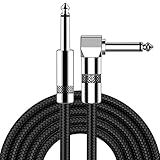
- [Low Noise High Fidelity] New bee guitar cord with 22AWG oxygen-free-copper center conductors provides enhanced signal transfer, the PVC insulation material and the high-density stranded copper double shield provide noise rejection for quiet operation
- [Ideal for Choice] New bee 1/4 straight and right angle metal connectors, ensures a secure connection in any instrument, pedal, or amp jack. L shape great fro on stage guitar stands
- [Wide Compatible] Suitable for mixer, power amplifier, microphone, effector, decoder, equalizer, electoronic organ, electric guitar, electric bass and other electronic equipments. Widely used in the installation of smart home, karaoke speaker, professional stage audio, etc
- [Easy Disassemble] Making incidental repairs quick and easy! Very nice, flexible cable
- [Dont Hesite to Order] 24 hours customer services and professional technology team are standing by
CRS does not occur in every patient, and its severity cannot be predicted from the treatment name alone. Clinicians grade the syndrome, monitor vital signs and laboratory results, and may use supportive care or immune-modulating medicines. With bispecific antibodies, incidence and timing vary with the product, disease subtype, route, and dosing schedule. With CAR T, CRS is a well-established early complication that requires a center experienced in rapid recognition and treatment.
Neurologic toxicity and ICANS
CAR T-associated neurologic toxicity can include confusion, unusual sleepiness, difficulty finding words, impaired speech, tremor, or seizures. NCI identifies ICANS as an important CAR T toxicity (NCI CAR T-cell information). Neurologic checks are therefore part of post-infusion monitoring, and patients may be instructed not to drive or operate machinery for a period specified by their treatment team.
Bispecific antibodies can also cause neurologic effects, but ASH consensus recommendations describe neurotoxicity as generally less common and lower grade than CAR T-associated ICANS. That is a population-level observation, not a guarantee for an individual; product, dose, disease, and patient factors still matter (ASH consensus recommendations).
Infections and low blood counts
Both treatments can weaken immune defenses. Low white-cell, red-cell, or platelet counts may follow lymphodepleting chemotherapy, CAR T infusion, repeated bispecific dosing, or the cancer itself. B-cell-directed therapies can reduce normal B cells and antibody levels, increasing susceptibility to infection. Teams may use antimicrobial prevention, immunoglobulin replacement, growth-factor support, transfusions, or treatment delays according to the patient’s risk.
Other serious effects
Patients can experience fatigue, fever, infusion or injection reactions, organ complications, tumor lysis, prolonged cytopenias, and worsening of existing health problems. The precise risk profile comes from the specific product label and the patient’s medical history, not from the treatment category alone.
FDA warning for certain CAR T products
On April 18, 2024, FDA required boxed-warning labeling for the risk of T-cell malignancies after treatment with currently approved BCMA-directed or CD19-directed genetically modified autologous CAR T-cell immunotherapies. FDA recommends lifelong monitoring for secondary malignancies (FDA safety communication). This warning applies to the specified approved CAR T products; it should not be generalized to every investigational cell therapy or to bispecific antibodies.
Rank #4

- Digital Family Calendar: BSIMB digital calendar wall touch screen puts an end to your chaotic life. Designed for busy families, the digital calendar keeps you organised and in step with your family. Assign different colours and tasks to each family member to make family scheduling easier and more intuitive.
- Easy Setup and Auto-Sync: Plug in, connect to WLAN and auto-syn your electric calendar in minutes. Digital wall calendar compatible with Google calendar, iCloud calendar, Outlook calendar, Cozi calendar and Yahoo calendar. Add events directly on the device or through the ecalendar app. Electronic calendar stays current whether you're at work or traveling—no manual updates needed.
- All-In-One Home Assistant: Smart calendar builds habits and encourage independence with personalised chores. Display daily meal plan to reduce the daily ‘What's for dinner?’ stress. To-do lists keep track of everything you want. Turning chores into valuable achievements with stars and rewards, making life easier and more enjoyable.
- Manage Anytime Anywhere: BSIMB electronic calendar for family stay connected with the powerful ecalendar app. Access and manage your digital wall calendar anytime, anywhere with free features like stars & rewards, photo screensaver, chore charts, meals plans, to-do lists etc. Electronic planner paid features like Magic Import tailor advanced tools for users with special needs.
- Stay in Touch with Loved Ones: Share photos or videos from your phone to electronic wall calendar with app, instantly update your life moment, and keep in touch with your family, especially those who are far away; you can also surprise your smart calendar digital wall by sending him a wish card; it's also great for keeping tech-illiterate elders in touch with the youngsters.
What the comparative evidence actually shows
The large B-cell lymphoma result
An ASH commentary published August 8, 2024, summarized a meta-analysis of studies in third-line-or-later large B-cell lymphoma. The pooled CAR T studies showed higher complete-remission and progression-free-survival rates than the pooled bispecific-antibody studies, alongside more adverse events (ASH commentary).
PC Slower Than It Used to Be?
A free scan shows the junk files, broken settings and background clutter dragging Windows down - then fixes them in one click.Free scan · Windows 10 & 11Outdated Drivers Are Slowing You Down
One free scan finds every outdated or missing driver and matches the right update for your exact hardware.Free scan · exact hardware matchThe summary did not provide effect-size figures in the cited material, and the comparison was not randomized. Patients in separate studies can differ in age, disease burden, prior therapies, eligibility criteria, follow-up time, supportive care, and response assessment. Those differences can influence pooled results. The finding is useful context for that treatment setting, but it cannot prove that CAR T is superior for every person.
Why the same conclusion cannot be carried to every cancer
CAR T and bispecific products recognize different targets and have different approved indications. Evidence in third-line large B-cell lymphoma does not settle the choice in multiple myeloma, leukemia, other lymphoma subtypes, earlier treatment lines, or clinical trials. A result also may change as products move earlier in treatment or as newer regimens become available.
What a fair comparison requires
- The same cancer subtype and target.
- The same treatment line and prior therapies.
- Comparable patient health, disease burden, and response criteria.
- Similar follow-up duration and definitions of progression and toxicity.
- Randomized head-to-head data when the question is whether one treatment is better than another.
Eligibility is product- and patient-specific
For CAR T
Eligibility can depend on the exact diagnosis, target antigen, prior treatment history, age, performance status, organ function, infection status, disease tempo, and the product’s regulatory label. NCI reports six approved CAR T therapies for blood cancers, but the number of approved options does not mean that all six are interchangeable (NCI treatment information). The FDA label for each product defines its indication and important restrictions; for example, product labeling is available through FDA’s cellular and gene-therapy resources (FDA product information example).
For bispecific antibodies
Eligibility likewise depends on the cancer target, disease subtype, prior therapies, treatment line, organ function, infection risks, and the individual product’s label. A bispecific may be unsuitable if the target is absent, if an uncontrolled infection or organ problem makes immune activation unsafe, or if another therapy is more appropriate for the disease stage.
Health and logistics matter
Both approaches require a center with experience in immune-effector therapies, emergency response, laboratory monitoring, and infection management. The patient’s ability to remain near the center, have a caregiver when required, and return quickly for evaluation can affect feasibility. Costs, insurance rules, travel requirements, and appointment frequency vary by location and individual coverage; the available evidence does not establish a universal comparison, so those details must be confirmed with the treating center and insurer.
How clinicians frame the choice
| Question | Why it matters |
|---|---|
| What is the exact cancer subtype and target? | Approvals and evidence are target- and disease-specific. |
| Which treatment line is being considered? | Results in third-line-or-later large B-cell lymphoma cannot automatically be applied earlier or to another cancer. |
| How quickly must treatment begin? | CAR T includes collection and individualized manufacturing; bispecific therapy can avoid that step but still requires evaluation and scheduling. |
| Is the patient fit for lymphodepleting chemotherapy and CAR T monitoring? | Organ function, infections, blood counts, neurologic status, and caregiver or travel requirements influence safety. |
| What is the dosing burden? | CAR T centers on one engineered-cell infusion followed by monitoring; bispecific therapy generally requires repeated doses and laboratory visits. |
| Which risks are especially important for this patient? | Prior neurologic disease, infection history, low blood counts, organ impairment, and disease burden can change the risk discussion. |
| What evidence applies to this exact situation? | Randomized trials, single-arm studies, real-world reports, and pooled comparisons answer different questions. |
This framework does not select a therapy on its own. It helps ensure that the discussion compares like with like rather than treating “CAR T” or “bispecific” as a single, uniform medicine.
Questions to bring to an oncology appointment
- What is my cancer’s exact subtype, target, and treatment line?
- Which CAR T products or bispecific antibodies are approved or being studied for this situation?
- How strong is the evidence for this option in patients with my prior treatments and health conditions?
- If CAR T is considered, how long is the expected interval from collection to infusion, and what happens if the disease changes during manufacturing?
- Would treatment require hospitalization, a caregiver, or staying near the center?
- What is the step-up schedule or observation plan for a bispecific antibody?
- How will CRS, neurologic symptoms, infections, and low blood counts be monitored and treated?
- What restrictions apply to driving, work, travel, or being far from emergency care?
- What long-term monitoring is required, including the FDA-recommended lifelong surveillance for secondary malignancies after specified CAR T products?
- What are the expected out-of-pocket costs and insurance authorization steps for my location?
When to contact the treatment team urgently
After either therapy, the treatment center should provide a written emergency plan and a 24-hour contact number. Symptoms that can signal CRS or neurologic toxicity include fever, chills, dizziness, faintness, rapid heartbeat, breathing difficulty, confusion, unusual sleepiness, trouble speaking, or a new seizure. New symptoms can also reflect infection or another complication. Patients and caregivers should follow the center’s instructions rather than trying to determine the cause at home.
Because the timing and severity of complications vary, the absence of symptoms after an early dose does not eliminate later risk, and a mild symptom should not be assumed to be harmless without clinical guidance.
Free tools Windows power users keep installed
One-click scans. No signup required.
Bottom line for comparing the two approaches
CAR T-cell therapy creates a living, patient-specific treatment through cell collection, laboratory engineering, expansion, and infusion. Bispecific antibodies recruit the patient’s existing T cells through repeated doses of an engineered antibody. CAR T can involve a manufacturing wait and intensive early monitoring; bispecific therapy avoids individualized manufacture but usually requires ongoing dosing and visits. Both can cause CRS and infections, while CAR T has a distinctive ICANS risk and specified FDA boxed-warning requirements for T-cell malignancies.
The strongest comparative signal cited here—higher pooled complete-remission and progression-free-survival rates with more adverse events—comes from third-line-or-later large B-cell lymphoma and non-randomized pooled studies. It should inform, not replace, an individualized discussion of diagnosis, prior treatment, urgency, health status, logistics, and preferences with an experienced oncology team.
Quick Recap
Product prices and availability are accurate as of the date/time indicated and are subject to change. Any price and availability information displayed on Amazon at the time of purchase will apply.

