3D visualization is usually the better choice for laparoscopic work that depends on precise depth judgment and instrument navigation. In a 2023 systematic review of 25 randomized trials involving 3,003 patients, 3D laparoscopy shortened operative time, but it did not produce statistically significant improvements in morbidity, mortality, conversion to open surgery or hospital stay. The practical answer is therefore workflow-specific: 3D can improve how a team performs a technically demanding task without proving that every patient outcome is better.
Two-dimensional imaging remains sensible when a department values simplicity, broad compatibility and familiar ergonomics. Augmented-reality (AR) overlays are a separate, less mature category: they can improve navigation metrics in preclinical experiments, yet poorly designed overlays can hide unexpected anatomy and create serious attention failures.

As an Amazon Associate I earn from qualifying purchases.
The short answer: choose for the task, not the headline
Operating-room imaging has two different questions that are often blended together:
- Can the surgeon see and manipulate anatomy more precisely? This is where stereoscopic 3D has its clearest advantage.
- Does that technical advantage improve patient outcomes? Current comparative evidence does not establish a universal 3D benefit for complications, deaths, conversion or length of stay.
For minimally invasive procedures involving fine dissection, suturing or navigation around structures at different depths, 3D supplies separate images to the two eyes and restores a stereoscopic cue that 2D video lacks. That can reduce the mental effort required to infer distance. The gain is not automatic: viewing distance, stereoacuity, display quality, task design and surgeon experience all affect the result.
#1 Best Overall

- [Ultra-Lightweight Ear Buds Designed for Small Ears] Each earbud weighs only 3.7g and features a compact, ergonomic in-ear design made especially for small ears. Secure, low-profile, and comfortable for workouts, all-day wear or overnight sleeping.The ultra-slim profile sits flush in your ear with no hard edges poking or rubbing, so you can even sleep on your side without discomfort.
- [Immersive Stereo Sound with TOZO OrigX Technology] TOZO OrigX tuning delivers clear vocals, balanced mids, and natural stereo sound for music, podcasts, and videos.
- [Long Battery Life for Daily Use] Get up to 7 hours of playtime on a single charge, with up to 32 hours total using the charging case—ideal for workdays, commuting, and extended listening sessions.
- [Bluetooth 5.3 & Stable Connection] Bluetooth 5.3 provides fast pairing, stable wireless performance, and reduced dropouts as you move around home or office.
- [Deep Bass with Clear Vocals] High-performance drivers produce punchy bass while keeping vocals clean and detailed for everyday listening.
A 2D system can still be the rational choice when the clinical workflow does not depend heavily on depth discrimination or when the institution cannot justify added calibration, integration and training demands. A department should identify a specific problem—such as repeated difficulty judging depth during laparoscopic navigation—then test whether 3D solves it reliably.
What the strongest comparative evidence actually shows
Technical performance in the British Journal of Surgery study
A comparative study published in the British Journal of Surgery in 2017 measured depth judgment, task completion and perceived workload with 3D and 2D displays. The clearest gains occurred in depth perception, especially at a close viewing distance.
| Measure | Result with 3D compared with 2D | Study qualification |
|---|---|---|
| Precision of depth judgments at 1 metre | 6.2 times more precise | Comparative display study, BJS, 2017 |
| Precision of depth judgments at 3 metres | 3.0 times more precise | Comparative display study, BJS, 2017 |
| Task-completion time | Up to 64% shorter | Task performance result, BJS, 2017 |
| Perceived workload | Up to 34% lower | Task performance result, BJS, 2017 |
The distance effect matters. A display that delivers a substantial depth benefit at one metre may provide a smaller, though still measurable, benefit when the viewer is farther away. This is one reason a result from a controlled display task should not be converted directly into a promise about every operating room.
Do these 3 things before closing this tab:
1Clear out junk files and repair common Windows errors2Fix the driver behind crashes, sound loss and screen glitches3Repair Windows errors before they cause bigger problemsThe study’s conclusion was that “3D displays offer large improvements over 2D displays in precision of depth judgements, technical performance and perceived workload.” Those findings support using 3D where the bottleneck is spatial judgment. They do not, by themselves, demonstrate fewer complications or better recovery.
Operative time in the 2023 randomized-trial review
A 2023 systematic review in Annals of Surgery Open pooled 25 randomized trials with 3,003 patients undergoing laparoscopic procedures. Across those trials, 3D vision was associated with an 8.0% reduction in operative time compared with 2D. The review also reported that the majority of surgeons favored 3D vision in 13 of the 15 trials that measured preference.
An average time advantage is operationally relevant: shorter procedures can increase schedule flexibility and reduce the period during which a patient is anesthetized. However, the review’s patient-outcome results did not show a statistically significant superiority for 3D.
| Patient outcome | 3D laparoscopy | 2D laparoscopy | Interpretation from the review |
|---|---|---|---|
| Morbidity | 14.9% | 13.5% | No significant difference |
| Mortality | 0% | 0% | No significant difference |
| Conversion to open surgery | 0.8% | 0.9% | No significant difference |
| Hospital stay | 9.6 days | 10.5 days | No significant difference |
These figures should be read as evidence about the populations and procedures included in the randomized trials, not as a guarantee for an individual operation. The absence of a significant difference does not prove that the systems are identical in every clinical situation; it means the review did not establish a reliable patient-outcome advantage for 3D.
Rank #2

- 【IP68 Waterproof Multifunctinal Smart Watch】Torjalph fitness activity tracker smart watch is IP68 waterproof technology ,you can wear it when swimming,handwashing,it's rain-proof which means that you perform multiple exercise modes outside without worrying about sweat or rain corroding your fitness smart watch,and this watch equipped with a 230 mAh large capacity battery magnetic charging ,and this sports activity tracker watch can be used 5-7 days If fully charged.
- 【Larger 1.83'' Full Screen Watch & Multi-dial Selection】1.83 inch full HD color touch screen smart watch for men / women provides excellent 240*284 resolution image quality ,This Bluetooth smart watch offers a better touch experience and remarkable immersion and ,more than 200 watch faces for you to choose from App"Da Fit ", you can change the dial style according to your mood to wear keeping the world on your wrist
- 【Accurate Activity Tracker Smart Watch 】sports watch activity tracker uses sweat and dust resistant breathable silicone strap, our Fitness Tracker Smart Watch for Android iOS Phones supports 12 sports modes,walking,running,bicycle,swimming,badminton,basketball,football,rope skipping. This bluetooth calls smart watch for men women is lightweight and stylish, bringing more convenient and relaxing sports experience while also providing more protection.
- 【Your 24 Hour Personal Daily Health Monitor】Fitness watch for women men full touch screen IP67 waterproof bluetooth smartwatch for Android iOS Phones with heart rate blood pressure monitor multifunction Andriod smart watch with steps counter sleep monitor sports fitness watch, monitoring blood oxygen saturation allows you to understand your physical condition in real time to track fitness progress ,to know your health status in time.
- 【More Functions Bluetooth Call Smart Watch】This fitness activity smart watch full screen for iPhone and Android phones includes a bunch of new features including:The bluetooth smart watch can hang up the phone, receive and display WhatsAPP /Text /Facebook /Twitter /Messenger reminder.Support sedentary reminder, alarm clock, stopwatch, timer,weather information,music control, remote camera control compatible with Android 5.0 and above or iOS 9.0 and above smartphones.
Why better depth perception does not automatically mean safer surgery
Depth cues are one component of safe surgery. A surgeon must also recognize anatomy, choose a safe dissection plane, control bleeding, coordinate with the team and respond to unexpected findings. A display can make a specific manipulation easier while leaving those other determinants unchanged.
The available evidence separates into two layers:
- Simulated or controlled technical tasks: These show large improvements in depth precision, speed and workload under defined conditions.
- Clinical patient outcomes: The randomized-trial review found a time advantage but no significant difference in the reported morbidity, mortality, conversion or hospital-stay measures.
That distinction prevents two common errors. First, it is too strong to say that 3D is universally safer. Second, it is too dismissive to say that a technical improvement has no clinical value simply because a broad outcome difference was not detected. In a procedure where a surgeon repeatedly needs to judge the distance between an instrument and delicate anatomy, improved control may be valuable even when a trial is not powered to show a change in complication rates.
How 3D affects speed, workload and surgeon preference
Faster tasks are not the same as faster operations
The BJS work measured task completion under controlled conditions, with improvements of up to 64% for the tested tasks. The 2023 clinical review measured operative time across real procedures and found an 8.0% reduction. Those are related but different endpoints. A short laboratory task isolates visual-motor performance; an operation includes preparation, anesthesia, positioning, dissection, hemostasis, specimen handling and closure.
When evaluating a local business case, keep both levels visible. A team may see clear gains during suturing practice yet obtain a smaller effect on total room time because other steps dominate the case. Conversely, a procedure composed largely of depth-sensitive maneuvers may be more responsive than the average across several procedure types.
Free tools Windows power users keep installed
One-click scans. No signup required.
Workload and preference
The controlled BJS study found up to 34% lower perceived workload with 3D. Lower workload can matter during long or technically dense cases because visual effort is one part of the surgeon’s overall cognitive demand. It should not be treated as a substitute for fatigue measurement, clinical judgment or team communication.
In the randomized-trial review, most surgeons favored 3D in 13 of 15 preference-reporting trials. Preference is useful implementation evidence: adoption is easier when clinicians perceive a system as helpful. It is not proof of patient benefit, and preference can be influenced by novelty, prior training and the specific procedure shown.
Disadvantages and failure modes of 3D visualization
It is more dependent on viewing conditions
The size of the benefit depends on the optical setup. The BJS results varied with viewing distance, and the 2017 comparative display study in the British Journal of Surgery reported that stereoacuity, display quality, task design and surgeon experience also influence the result. A system that performs well in a demonstration may deliver less value if the room layout, screen position or image quality differs from the evaluation conditions.
Rank #3
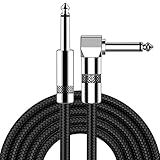
- [Low Noise High Fidelity] New bee guitar cord with 22AWG oxygen-free-copper center conductors provides enhanced signal transfer, the PVC insulation material and the high-density stranded copper double shield provide noise rejection for quiet operation
- [Ideal for Choice] New bee 1/4 straight and right angle metal connectors, ensures a secure connection in any instrument, pedal, or amp jack. L shape great fro on stage guitar stands
- [Wide Compatible] Suitable for mixer, power amplifier, microphone, effector, decoder, equalizer, electoronic organ, electric guitar, electric bass and other electronic equipments. Widely used in the installation of smart home, karaoke speaker, professional stage audio, etc
- [Easy Disassemble] Making incidental repairs quick and easy! Very nice, flexible cable
- [Dont Hesite to Order] 24 hours customer services and professional technology team are standing by
It adds implementation complexity
Compared with a conventional 2D feed, a stereoscopic workflow requires the two eyes’ views to remain correctly separated and synchronized. A department evaluating 3D should therefore include calibration and compatibility checks in its acceptance process, rather than treating the monitor as a drop-in replacement. Integration with existing cameras, recording, routing and other imaging sources must be verified on the actual equipment used in the room.
It does not remove the need for training
3D can reduce the visual difficulty of a task, but surgeons still need to learn the procedure, the instruments and the display system. Training should include the intended clinical workflow, not only a product demonstration. Teams should define how to revert to 2D if the stereoscopic image is unavailable or poorly calibrated.
Capital cost is only one part of ownership
No reliable cost-effectiveness conclusion is established by the cited evidence. A purchasing decision should account for acquisition, installation, service, calibration, staff training, compatibility work and any replacement or backup equipment. The relevant comparison is total cost of ownership against the cases in which the department expects a meaningful technical or time benefit—not the monitor’s purchase price alone.
When 2D imaging remains the sensible choice
2D is a reasonable choice when the workflow prioritizes:
- Simple setup and familiar operating-room ergonomics.
- Broad compatibility with existing imaging and recording equipment.
- Lower implementation and training complexity.
- Procedures in which stereoscopic depth is not the principal technical bottleneck.
- A clinical environment that needs a dependable fallback or uses several image sources that are not all available in 3D.
The evidence does not show universal patient-outcome superiority for 3D. Therefore, a hospital should not replace a functioning 2D system solely because 3D is newer or because a laboratory demonstration looks impressive. The justification should identify the cases, maneuvers and users for whom the added capability is expected to matter.
The Tool Desk
Outbyte Driver Updater FREEScan for outdated or missing drivers - takes under a minuteDriver Scan →Outbyte PC Repair FREEClear out junk files and repair common Windows errorsFree Scan →Is augmented reality ready for routine surgery?
What preclinical navigation evidence shows
AR overlays place computer-generated guidance over the operative view. In a preclinical randomized study of 50 novice surgeons, image guidance shortened task time and tool paths. That result suggests that an overlay can help a user follow a planned route or target.
The same experiment exposed a serious safety trade-off. Solid overlays produced severe inattentional blindness: users could focus on the guidance and fail to notice an unexpected finding. Wire-mesh and inverse-realism overlays reduced the risk in that study but did not eliminate it. An overlay that is visually persuasive can therefore be more dangerous than one that is obviously separate from reality if it encourages the user to ignore information outside the guided region.
Rank #4

- Digital Family Calendar: BSIMB digital calendar wall touch screen puts an end to your chaotic life. Designed for busy families, the digital calendar keeps you organised and in step with your family. Assign different colours and tasks to each family member to make family scheduling easier and more intuitive.
- Easy Setup and Auto-Sync: Plug in, connect to WLAN and auto-syn your electric calendar in minutes. Digital wall calendar compatible with Google calendar, iCloud calendar, Outlook calendar, Cozi calendar and Yahoo calendar. Add events directly on the device or through the ecalendar app. Electronic calendar stays current whether you're at work or traveling—no manual updates needed.
- All-In-One Home Assistant: Smart calendar builds habits and encourage independence with personalised chores. Display daily meal plan to reduce the daily ‘What's for dinner?’ stress. To-do lists keep track of everything you want. Turning chores into valuable achievements with stars and rewards, making life easier and more enjoyable.
- Manage Anytime Anywhere: BSIMB electronic calendar for family stay connected with the powerful ecalendar app. Access and manage your digital wall calendar anytime, anywhere with free features like stars & rewards, photo screensaver, chore charts, meals plans, to-do lists etc. Electronic planner paid features like Magic Import tailor advanced tools for users with special needs.
- Stay in Touch with Loved Ones: Share photos or videos from your phone to electronic wall calendar with app, instantly update your life moment, and keep in touch with your family, especially those who are far away; you can also surprise your smart calendar digital wall by sending him a wish card; it's also great for keeping tech-illiterate elders in touch with the youngsters.
Why registration and attention are central risks
AR is only as trustworthy as the alignment between the virtual model and the patient. Registration errors, image distortion, blur and changes in viewpoint can make guidance misleading. Attention management is equally important: the display must help the user notice new anatomy, bleeding or other findings rather than narrowing attention to the planned overlay.
These are not merely interface preferences. A navigation aid that is slightly misaligned or that masks an unexpected structure can change a clinical decision. Safe evaluation should therefore test failure cases and off-plan findings, not just successful completion of a planned path.
What’s actually slowing this PC down?
Pick the symptom - the matching free tool is one click away.
Clinical maturity of optical see-through headsets
A 2022 systematic review from University College London examined optical see-through AR head-mounted displays. It reported increasing research activity but concluded that the devices were not yet established in operating rooms and that clinical-benefit studies were lacking. The review also identified unresolved questions around registration accuracy, ergonomics and cost-effectiveness.
That evidence supports treating AR as an investigational or tightly controlled capability rather than a routine replacement for conventional surgical imaging. A hospital considering a pilot should define supervision, fallback visualization, data recording and stopping criteria before clinical use.
Independent reader supportYour contribution helps us test, update, and keep practical guides available for everyone.What immersive 3D contributes to education
Immersive 3D may have a role in teaching even when the case for changing clinical monitors is uncertain. A randomized trial of 231 fourth-year medical students compared the same 12-minute surgical video shown in immersive 3D through a head-mounted display with a conventional 2D video. The study measured knowledge retention, preparedness and engagement over one month.
This design supports discussing immersive 3D as a training and engagement tool. It does not prove that students who learn from immersive video will operate more safely, complete procedures faster or produce better patient outcomes. Education programs should keep those endpoints separate:
Recommended Free Tools
- Learning outcomes: retention, preparedness and engagement can be measured after instruction.
- Technical transfer: learners must still demonstrate skills in a realistic simulation or supervised clinical setting.
- Patient outcomes: these require clinical evidence and cannot be inferred from a viewing study.
A practical decision framework for an operating room
1. Define the visual problem
List the exact maneuvers in which surgeons report difficulty judging depth, aligning instruments or navigating narrow spaces. Avoid a general statement such as “better image quality”; specify the task that the system must improve.
2. Match the evidence to the endpoint
If the goal is faster manipulation or lower visual workload, use technical-task measures. If the goal is shorter operations, measure room and operative time in the relevant procedures. Do not claim a safety improvement unless the evaluation measures clinically meaningful safety outcomes.
3. Test the actual room configuration
Evaluate the display at the distances and positions used in practice. Check image quality, calibration, compatibility with the camera and routing chain, recording and the ability to continue safely in 2D if needed.
4. Include different users and procedures
Benefits can depend on surgeon experience and task design. A pilot should include the clinicians who will use the system and the procedures that motivated the purchase, rather than relying on a single expert demonstration.
PC Slower Than It Used to Be?
A free scan shows the junk files, broken settings and background clutter dragging Windows down - then fixes them in one click.Free scan · Windows 10 & 11Crashes, No Sound, or Screen Glitches?
Random freezes, missing sound and display glitches usually trace back to one bad driver. Find and replace yours safely.Free scan · under a minute5. Measure trade-offs as well as gains
Record task or operative time, errors, workload, preference, interruptions and any cases in which the team reverted to 2D. For AR, add registration accuracy, missed unexpected findings and the behavior of users when the overlay conflicts with the live view.
6. Set a threshold for adoption
Decide in advance what improvement would justify the added cost and complexity. If the system does not solve the defined workflow problem, retaining 2D is a valid outcome.
How to compare 3D, 2D and AR without conflating them
| Decision axis | 3D stereoscopic display | 2D display | AR overlay |
|---|---|---|---|
| Depth judgment | Strongest evidence of improvement, including 6.2-fold precision at 1 metre and 3.0-fold at 3 metres in the BJS study | Requires the user to infer depth from available 2D cues | Can add planned spatial guidance, but accuracy depends on registration |
| Task or operative time | Up to 64% shorter controlled tasks; 8.0% shorter operative time in the 2023 review | Comparator condition in those studies | Shorter task time and tool paths in a preclinical study of 50 novices |
| Patient outcomes | No significant difference from 2D for the outcomes reported in the 2023 review | Reference condition in that review | Clinical benefit not established by the cited reviews |
| Workload | Up to 34% lower perceived workload in the BJS study | Higher workload in the compared tasks | Attention can be redirected in ways that create inattentional blindness |
| Implementation concerns | Calibration, display quality, viewing distance and integration must be managed | Simpler compatibility and familiar workflow | Registration, blur, distortion, ergonomics and attention management remain unresolved |
| Evidence maturity | Comparative technical evidence and randomized clinical trials exist | Established comparator technology | Increasing research, but not established for routine operating-room use |
What a procurement team should ask vendors and clinicians
- Which named procedures and maneuvers are expected to improve, and how will improvement be measured?
- At what viewing distances was the system evaluated, and do those distances match the operating room?
- How is stereoscopic calibration checked before a case, and what is the procedure if calibration fails?
- Which cameras, routing equipment, recorders and other imaging sources are compatible?
- What training is required for surgeons, assistants, nurses and technical staff?
- How quickly can the team switch to a 2D view if the stereoscopic or overlay image is unavailable?
- For AR, how is registration verified, how are unexpected findings kept visible and how is an overlay disabled immediately?
- What local data will be collected on time, workload, errors, preference, interruptions and patient outcomes?
- What service, maintenance and replacement arrangements determine total ownership cost?
Bottom line for operating-room leaders
Choose 3D when a defined minimally invasive workflow repeatedly depends on fine depth judgment and the department can validate the system in its actual room configuration. The best evidence supports better technical performance, lower perceived workload and a meaningful reduction in operative time, while the randomized clinical evidence does not show a universal advantage in morbidity, mortality, conversion or hospital stay.
Keep 2D when simplicity, compatibility and predictable operation outweigh a task-specific depth benefit. Treat AR as a controlled development area: preclinical navigation gains are promising, but solid overlays can cause inattentional blindness and routine clinical benefit remains unproven. The right purchase is the one that solves a measured workflow problem without obscuring the limits of the evidence.
Quick Recap
Product prices and availability are accurate as of the date/time indicated and are subject to change. Any price and availability information displayed on Amazon at the time of purchase will apply.

